Archive for category: News

Holiday Season Tips for Assisted Living & RCFE Communities: Joy, Safety, and Compliance

The holiday season spanning Thanksgiving, Hanukkah, Christmas, Kwanzaa, and New Year’s is one of the most critical times of the year for Residential Care Facilities for the Elderly (RCFEs) and assisted living communities. It is a period filled with deep emotion, family reunions, and festive traditions, but it is also a time when your community experiences high visibility from visitors, family members, referral partners, and California Department of Social Services (CDSS) Community Care Licensing Division (CCLD) inspectors.

With strategic planning, your facility can create meaningful experiences that promote resident well-being, strengthen family trust, and showcase the highest standards of care and Title 22 compliance.

1. Designing Inclusive Holiday Activities

A well-balanced activity schedule sets the tone for the entire season. Offer a variety of festive events, such as Thanksgiving gratitude circles, Christmas cookie decorating, Hanukkah menorah lighting celebrations, hot cocoa socials, holiday movie marathons, and themed photo booths.

Adapting for Memory Care & High Acuity

Ensure activities are tailored to accommodate residents with varying cognitive abilities and mobility limitations:

  • Sensory-Friendly Events: Use tactile, auditory, and visual cues like holiday music, scent stations (cinnamon, pine), and simple crafts.
  • Quiet Spaces: Holiday bustle can trigger overstimulation, agitation, or exit-seeking behavior in residents with dementia. Maintain quiet, low-sensory zones where residents can relax or meet privately with visitors.
  • One-on-One Engagement: Provide room visits, gentle reminiscence therapy, or audiobooks for residents who prefer not to attend large group gatherings.

2. Prioritizing Fire Safety, Infection Control, and Title 22 Compliance

Winter celebrations coincide with peak respiratory virus season and heightened scrutiny from local Fire Marshals and CCLD inspectors. Protecting resident safety requires adhering strictly to state codes and licensing rules.

California RCFE Fire Safety Standards

  • Artificial Trees Only: Live-cut Christmas trees are generally prohibited in RCFE settings due to fire hazards. Ensure all artificial trees and greenery are certified flame-retardant.
  • 30% Wall Rule: Holiday decorations must not cover more than 30% of any wall or door surface area to comply with Life Safety Code and Title 24 standards.
  • Egress & Alarms: Never obscure exit signs, emergency pull stations, fire extinguishers, or egress pathways with garlands, lights, or displays.
  • Flameless LED Candles: Open flames are prohibited in RCFEs under California fire codes. Use battery-operated LED candles for Menorahs, Advent wreaths, or table displays.

Infection Mitigation & Resident Rights

  • Triple Epidemic Protection: Reinforce infection control protocols for flu, RSV, and COVID-19. Provide visible hand sanitizer stations, encourage voluntary screening at entry points, and promote staff vaccination.
  • Resident Rights (Title 22 § 87468): While safety is paramount, visitation rights cannot be arbitrarily restricted without an official public health directive or active outbreak protocol. Offer clear guidance to families without violating resident visitation rights.
  • Indoor Climate Control: Ensure HVAC systems meet Title 22 § 87572 standards, maintaining indoor room temperatures between 68°F and 85°F during cold snaps.

3. Dementia-Informed Care & Reappraisal Triggers (LIC 625)

The holidays bring changes in routine, increased noise, and unfamiliar guests, which can cause confusion or emotional distress for residents with dementia or memory loss.

  • Train Staff on Redirection: Ensure caregivers across all care levels are trained in dementia-sensitive care, validation techniques, and quiet transitions.
  • Reappraisal Triggers: Title 22 requires a prompt Reappraisal (Form LIC 625) whenever a resident experiences a significant change in physical, mental, or functional status. Monitor residents closely for increased fall risks, rapid weight changes, or acute confusion triggered by holiday disruptions.
  • Therapeutic Diet Compliance: Ensure festive holiday meals, from Thanksgiving turkey dinners to Christmas treats, strictly follow Title 22 § 87555 guidelines regarding texture modifications, diabetic needs, and physician-ordered therapeutic diets.

4. Engaging Families with a Holiday Visitor Guide

Proactive communication with families reduces confusion, streamlines visits, and reinforces your community’s professionalism.

What to Include in Your Holiday Family Guide:

  • Visiting Hours & Check-In: Detail entrance procedures, infection screening protocols, and peak visiting hours.
  • Dining & Space Reservations: Provide clear procedures for booking private dining rooms or joining communal Thanksgiving or Christmas meals.
  • Safe Gift Ideas: Offer guidance on appropriate gifts, avoiding items that present tripping hazards, fire risks, or diet contraindications.
  • Virtual Connection Options: Set up video call assistance for out-of-town family members so they can participate in holiday festivities remotely.

5. Leveraging Holiday Respite Stays and Community Marketing

The holiday season is an ideal opportunity to highlight your care standards to prospective families and referral sources.

  • Holiday Respite Admissions: Short-term respite stays allow caregivers to travel or rest while giving families a chance to experience your facility. Ensure all respite admissions complete the required pre-admission appraisal (LIC 603), medical assessment (LIC 602A), and TB clearance prior to move-in.
  • Storytelling & Consent: Capture uplifting holiday moments, photo ops, and resident stories for your newsletter, social media, and website. Always ensure signed photo/media release consents are on file.

Assisted Living & RCFE Communities Holiday Season Questions & Answers

What are the key fire safety rules for holiday decorations in a California RCFE?

Artificial trees must be labeled flame-retardant (live-cut trees are prohibited), decorations cannot exceed 30% of wall coverage, egress routes and fire equipment must remain unobstructed, and open flames/real candles are strictly banned in favor of battery-operated LED alternatives.

How can RCFE staff support residents experiencing grief or depression during Thanksgiving and Christmas?

Staff should conduct regular one-on-one check-ins, offer small-group reminiscence sessions, create memory boards, and normalize feelings of loss. Providing quiet spaces and personal support helps residents process nostalgia and grief during high-emotion holidays.

Can an RCFE restrict family visitation during the holiday respiratory virus season?

Under Title 22 § 87468 (Resident Rights), facilities cannot broadly restrict family visitation unless mandated by a local public health order or an active facility outbreak control protocol. Facilities should encourage voluntary screening and hygiene rather than imposing arbitrary bans.

What documentation is required for short-term holiday respite stays in an RCFE?

Respite residents require the same core licensing documentation as permanent residents, including a pre-admission appraisal (LIC 603), a completed medical assessment (LIC 602A) signed by a physician, and documented TB screening prior to move-in.

How should holiday disruptions and behavioral changes be managed in memory care?

Staff should use dementia-informed redirection techniques and maintain predictable daily routines where possible. If holiday disruptions trigger a lasting change in cognitive or functional status, the facility must complete a Reappraisal (LIC 625) and update the resident’s Care Plan.

Ready to Elevate Your RCFE Compliance and Leadership?

Delivering exceptional resident care while navigating complex California licensing laws doesn’t have to be overwhelming. Whether you are preparing your team for seasonal shifts, staying current with CDSS Title 22 updates, or looking to earn and maintain your RCFE Administrator Certification, our expert-led training programs are designed for your success. Empower your staff with convenient online continuing education and industry-leading compliance support.

California RCFE Licensure: Requirements, Application Checklist & Regulations

Summary

  • Regulator: California Department of Social Services (CDSS) / Community Care Licensing Division (CCLD) under Title 22 and California Health & Safety Code.
  • Administrator Rules: Must be 21+, complete an 80-hour Initial Certification course, pass the state exam (≥70%), pass background checks, and earn 40 Continuing Education (CE) hours every 2 years.
  • Licensing Process: Step 1: Administrator Certification → Step 2: Component I Orientation → Step 3: LIC 200 Application & Fire Clearance → Step 4: Component II Analyst Interview → Step 5: Component III On-Site Inspection.
  • Key Compliance Focus: Sufficient 24/7 staffing with CPR/First Aid coverage, person-centered evaluations, annual routine medical visit documentation, and updated safety features (slip-resistant flooring, 105°F–120°F water temp).

Opening a Residential Care Facility for the Elderly (RCFE) in California requires navigating a structured regulatory process managed by the California Department of Social Services (CDSS) and enforced by the Community Care Licensing Division (CCLD) under Title 22, Division 6, Chapter 8 and the California Health and Safety Code.

Whether you plan to open a 6-bed residential care home or a 100+ bed assisted living community, this guide outlines everything you need to know about Administrator certification, facility licensing, staffing compliance, and maintaining licensure in California.

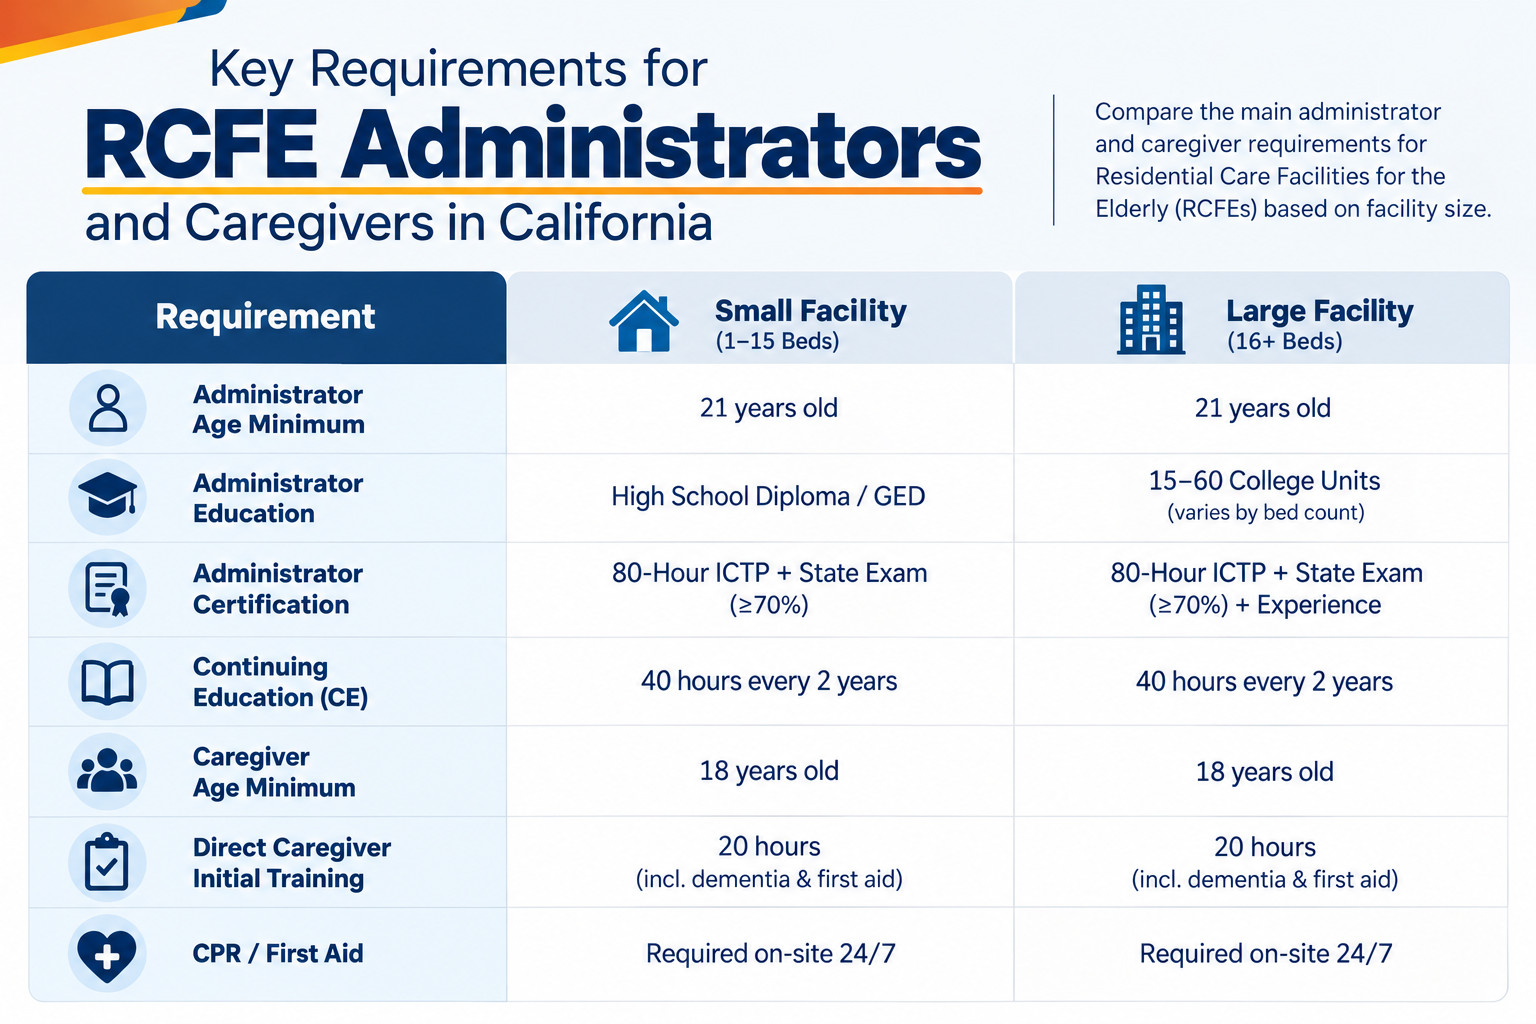
At a Glance: Key RCFE Requirements in California

RequirementSmall Facility (1–15 Beds)Large Facility (16+ Beds) 
Administrator Age Minimum21 years old21 years old
Administrator EducationHigh School Diploma / GED15–60 College Units (varies by bed count)
Administrator Certification80-Hour ICTP + State Exam (≥70%)80-Hour ICTP + State Exam (≥70%) + Experience
Continuing Education (CE)40 hours every 2 years40 hours every 2 years
Caregiver Age Minimum18 years old18 years old
Direct Caregiver Initial Training20 hours (incl. dementia & first aid)20 hours (incl. dementia & first aid)
CPR / First AidRequired on-site 24/7Required on-site 24/7


What is an RCFE License in California?

An RCFE (Residential Care Facility for the Elderly) license is a state-mandated authorization issued by the California Department of Social Services (CDSS) that allows a property or organization to provide housing, supervision, and non-medical care to adults aged 60 and older.

RCFEs provide support with Activities of Daily Living (ADLs)—including bathing, dressing, grooming, mobility, and medication management—for residents who do not require around-the-clock skilled nursing care.

The 6 Essential Steps to RCFE Licensure in California

1. RCFE Administrator Certification

Every RCFE must designate a certified Administrator responsible for daily operations, resident wellbeing, and regulatory compliance.

  • Initial Certification Training Program (ICTP): Candidates must complete an 80-hour CDSS-approved ICTP, which consists of 60 hours of live instruction (in-person or live virtual) and 20 hours of self-paced instruction.
  • State Examination: Within 60 days of course completion, candidates must pass the 100-question CDSS state exam with a score of 70% or higher.
  • Application Submission: Submit the Administrator application, background clearance, and state fees to CDSS within 30 days of passing the exam.
  • Administrator Education & Experience Prerequisites:
  • 1–15 Beds: High school diploma or GED.
  • 16–49 Beds: Minimum 15 college units + 1 year of eldercare experience.
  • 50+ Beds: Minimum 60 college units (2 years) + 3 years of eldercare experience.
  • Renewal: Certificates must be renewed every 2 years with 40 hours of Continuing Education (CE).

2. Mandatory Component I Orientation

Prior to submitting a facility application, prospective licensees must attend a 3-hour CDSS Component I Orientation specific to RCFEs. This orientation details state requirements, application compilation, and financial responsibility standards.

3. Facility License Application Submission

Applicants must submit a detailed LIC 200 Application for License along with a comprehensive Plan of Operation. Key requirements include:

  • Proof of property ownership or an executed lease agreement with explicit RCFE consent.
  • Detailed architectural floor plans showing resident rooms, bathrooms, and emergency exits.
  • Financial solvency documentation (proof of operating capital to cover startup and emergency expenses).
  • Local Fire Clearance approval (form LIC 850) obtained through the local fire authority.
  • Criminal background clearance (Live Scan) for all owners, Administrators, and staff.

4. Component II Licensing Interview

After submitting the written application, a CCLD Licensing Program Analyst (LPA) conducts a one-on-one Component II Interview with the applicant. This interview verifies operational readiness, financial comprehension, and knowledge of Title 22 standards.

5. Component III On-Site Inspection & Survey

Before approval, the LPA conducts an on-site physical survey of the property. The facility must strictly comply with physical plant standards:

  • Slip-Resistant Flooring: Flooring must meet modern safety standards (older “nonskid” wording updated).
  • Water & Safety: Water temperatures set between 105°F and 120°F; swimming pools/water features secured with a minimum 5-foot fence and self-latching gate.
  • First Aid & Emergency Supplies: Fully stocked medical and disaster preparedness kits on site.
  • Medication Storage: Double-locked central medication storage.

6. Staffing Compliance and Caregiver Ratios

California Title 22 does not set a rigid numeric staff-to-resident ratio for general care. Instead, law mandates sufficient staff at all times to meet the specific physical, mental, and safety needs of the current census.

  • Age Requirements: Administrators must be at least 21; direct care staff must be at least 18.
  • 24/7 Coverage: At least one staff member certified in CPR and First Aid must be on duty and on the premises at all times.
  • Caregiver Training: 20 hours of initial training before providing care (including 4 hours on dementia), plus 20 hours annually.
  • Dementia Care Staff: 8 hours of dedicated dementia training prior to care, plus 8 hours of annual CE.

Interactive RCFE Licensure Progress Checklist

RCFE LICENSURE STEP-BY-STEP ROADMAP

PHASE 1: ADMINISTRATOR CERTIFICATION

PHASE 2: FACILITY & APPLICATION PREPARATION

PHASE 3: INTERVIEW & INSPECTION

PHASE 4: POST-LICENSURE & ONGOING COMPLIANCE

Essential Title 22 Compliance Updates

  1. Person-Centered Language & Individualized Evaluations: California regulations require person-first language in documentation. Providers must evaluate access to items (e.g., razors or cleaning supplies) individually rather than restricting access based solely on a diagnosis.
  2. Annual Routine Medical Visits & Reappraisals: Under Section 87463, RCFEs must perform documented reappraisals whenever a resident experiences a significant change in physical, mental, or functional status—and at least once every 12 months. Facilities must document an annual routine medical visit with a licensed medical professional for all residents.
  3. Infection Control & Disaster Plans: Modern Title 22 inspections focus heavily on facility-specific infection control protocols, emergency evacuation strategies, and backup power plans.

Frequently Asked Questions

What is the difference between an RCFE and a Skilled Nursing Facility (SNF) in California?

An RCFE provides non-medical personal assistance, housing, and supervision with ADLs for seniors who do not require 24-hour nursing. A Skilled Nursing Facility (SNF) is a medical facility that provides 24/7 continuous skilled nursing care, medical treatments, and physical rehabilitation under medical supervision.

How long does it take to get an RCFE license in California?

The RCFE licensing process typically takes 6 to 12 months. Timeline factors include completing the 80-hour Administrator training, passing local fire clearance inspections, submitting the LIC 200 application packet, and completing state interviews and facility surveys.

What is the minimum staffing ratio for a 6-bed RCFE in California?

California law does not mandate a fixed numeric ratio for RCFEs. Title 22 requires “sufficient staff at all times” based on resident acuity. However, small 6-bed facilities typically maintain a 1:3 staff-to-resident ratio during waking hours, with at least one CPR/First Aid-certified staff member on site 24/7.

How many hours of continuing education do RCFE Administrators need?

RCFE Administrators must complete 40 hours of continuing education (CE) every two years to maintain active certification with the CDSS.

Need Expert Help Opening or Operating an RCFE?

Navigating CDSS application forms, preparing a custom RCFE Plan of Operation, and completing administrator certification can feel overwhelming. Assisted Living Education offers premier RCFE Administrator Initial Certification Training Programs, continuing education courses, and full-service licensing consultation to streamline your approval process.

Marketing Your RCFE in 2026: 7 Steps to Reach the Families Who Are Looking for You

Families researching assisted living now start with AI assistants, Facebook groups, and Reddit, not just Google. Keeping your RCFE full starts with making it easy for families to find and choose your community. That means maintaining a complete Google Business Profile, earning consistent reviews, participating in local online communities, creating a website that answers common questions, staying connected with families who may not be ready to move yet, and building strong referral relationships with discharge planners and hospice agencies.  Track where every inquiry comes from so you know what is working.

California’s senior population is growing, but that doesn’t mean families will automatically find your RCFE. Many facilities struggle to maintain occupancy because families are searching for care in new ways. They are turning to Google, online reviews, local communities, social media, and professional referral networks to find the right care for their loved ones. If your RCFE isn’t visible in those places, families may never know you’re there. 

This guide walks through seven practical steps for a new or established RCFE. It assumes you already meet state requirements, including an Administrator with a current RCFE Administrator Certification. If you are still working through licensing, start there, then come back to this article.

First, understand who is actually searching

Most RCFE inquiries do not come from the future resident. They come from an adult child, often a daughter in her 50s or 60s, who is stressed, short on time, and trying to make a good decision quickly. He/She is usually researching after a hospital discharge, a fall, or a diagnosis.

He/She starts online. Increasingly, he/she starts by asking an AI assistant like ChatGPT, Google’s AI Mode, or Perplexity something like “small assisted living homes near Anaheim that take residents with early dementia.” The family member may also post in a local Facebook group or a Reddit forum asking what other families have experienced.

Each step below focuses on your prospective resident’s family and where they are likely to look for care. 

1. Fix your Google Business Profile before anything else

For a six-bed home, your Google Business Profile (GBP) is often more important than your website. It is what shows up in Maps, in local search results, and in the sources AI assistants pull from when they recommend facilities.

Make sure it has:

  • The correct primary category (Assisted Living Facility) and accurate hours and phone number
  • A full description of who you serve, including care levels, whether you accept hospice, and whether you are licensed for dementia care
  • Recent photos of common areas, bedrooms, outdoor space, and staff
  • Answers to the questions families ask in the Q&A section
  • A short video walkthrough

Then keep it active. Post updates, add photos monthly, and respond to every review.

2. Build a system for earning more reviews

Reviews are the single most trusted signal families use, and they feed directly into AI-generated recommendations. Do not wait for them to happen.

Ask at natural moments: after a successful move-in, after a family visit that went well, at a 30-day check-in. Make it easy with a direct link. Never offer incentives, which violates Google’s policies and can damage trust.

Respond to every review, positive or negative, in a calm and specific way. A thoughtful reply to a critical review often does more for your credibility than another five-star rating.

Cover Yelp and the major senior care directories too. Caring.com, A Place for Mom, and SeniorLiving.org profiles are frequently cited by AI assistants, so keep your name, address, phone, pricing range, and services consistent everywhere.

3. Show up where families are already talking

This is the step most RCFE marketing guides skip, and it may be the highest-return one on this list.

Families often ask for recommendations in local Facebook groups, on Nextdoor, and in Reddit communities like r/AgingParents, r/dementia, and r/eldercare. They may also turn to caregiver support groups connected to hospitals, churches, and organizations such as the Alzheimer’s Association.

The right approach is to be helpful, not promotional. Answer questions honestly. Explain what an RCFE is versus a nursing home. Share what to look for on a tour. Tell people when your home is not the right fit. Over time, group members start recognizing your name and tagging you when someone asks.

Two cautions. Read each group’s rules before posting, since many ban self-promotion. And never discuss a specific resident or family, even vaguely.

4. Make your website answer families’ questions directly

Your website is still the place families go to confirm what they found elsewhere. It should load quickly on a phone and answer their most important questions in plain, easy-to-understand language:

  • Who you care for and what levels of care you provide
  • A base monthly rate or range, and what is included
  • What a typical day looks like, with a sample activity calendar and menu
  • Who the Administrator is, with a photo and their certification and background
  • How to schedule a tour, with a phone number and a form

Add a short FAQ page with clear, direct answers to common questions families ask. Well structured FAQ content can help search engines and AI tools better understand the information on your website. If you are comfortable adding structured data, consider using FAQ and LocalBusiness schema markup, or ask whoever manages your website to add it.

Publishing a price range may feel uncomfortable, but it can help families quickly determine whether your RCFE fits their budget. It also saves your team time by filtering out inquiries from families who are unlikely to be a good fit.

5. Start an email list, and consider Substack

Most families who tour do not decide immediately. Some are six months away. If you have no way to stay in touch, they forget you.

Collect email addresses at tours, community events, and on your website. Then send something useful once or twice a month: a short note on how residents spent the week, a tip on handling a difficult conversation with a parent, and a photo from a birthday celebration.

Substack is a free and simple place to start. It gives you a newsletter and a public archive of your posts that search engines can find, with no technical setup. Many families would rather read a warm, honest letter from a small home’s Administrator than a polished corporate blog.

Keep it simple and consistent. A short monthly update sent regularly is more efficient than an ambitious weekly newsletter that stops after a few issues.

6. Build your referral network

Digital marketing brings in families who are searching. Referral partners bring in families who have not started searching yet.

The most productive relationships for small RCFEs are usually hospital discharge planners, home health and hospice agencies, geriatric care managers, elder law attorneys, and placement agencies. Visit in person when appropriate, bring a one-page summary of who you serve and your current availability, and follow up when a bed becomes available.

Placement agencies typically charge a fee when they refer a resident. Understand those terms before signing anything.

7. Stay visible in your community

A small RCFE can host a holiday open house, a caregiver information evening, a resident art show, or a lawn party for the neighborhood. These do not need to be large. They need to be real, and they need to be photographed and shared on your Google Business Profile, Facebook, and newsletter afterward.

Community presence also builds the word-of-mouth that no ad can replace.

A note on what you can and cannot say

RCFE marketing in California comes with compliance responsibilities. You cannot imply medical or nursing care you are not licensed to provide. Advertising dementia or memory care has specific state requirements for staff training and disclosure. Photos of residents require consent. When in doubt, describe your services accurately and avoid making claims that could give families a misleading impression of the care you provide.

Track where inquiries come from

Add a “how did you hear about us?” question to every inquiry call and form. Tracking this information helps you see which marketing efforts are generating inquiries and where you may want to focus your time and resources. 

Highlight your training

Whether your Administrator recently completed continuing education or a new caregiver is working through required training, feature it on your website, GBP, and social channels. Families notice, and it sets you apart from homes that treat training as a box to check.

Assisted Living Education offers state-approved RCFE Administrator Certification, continuing education, and caregiver training. Contact us with questions or to enroll.

Additional RCFE Marketing Questions Answered

How do families use AI to find assisted living?

Families are increasingly using AI tools like ChatGPT or Google’s AI Mode to research senior care options and find information about local facilities. These tools draw on information from sources like Google Business Profiles, senior care directories, reviews, and facility websites. Keeping your RCFE information complete, accurate, consistent, and up to date can make it easier for these tools to understand your facility and the services you provide.

Can I promote my RCFE in Facebook groups and on Reddit?

Yes, if you follow each group’s rules and lead with genuinely helpful answers rather than promotion. Families in groups like r/AgingParents and local caregiver communities value honest guidance. Over time, that builds the recognition that leads to referrals.

Should a small RCFE have a newsletter?

Yes. Most families who tour are not ready to decide. A short monthly email or Substack post keeps your home top of mind. Substack is free, requires no technical setup, and its public posts can also be found in search.

What can an RCFE say about dementia care in its marketing?

Your marketing should accurately describe the dementia-related care, services and programs your RCFE is licensed and able to provide. California has specific requirements before a facility can advertise dementia or memory care. Describe your actual capabilities plainly and avoid implying medical or nursing services you do not offer.

How do I get more reviews for my RCFE?

Ask for a review at natural moments, such as after a successful move-in or a positive family visit, and provide a direct link. Never offer incentives. Respond to every review, including critical feedback, with a professional and helpful response. Your responses are visible to prospective families and can help demonstrate how your RCFE communicates with families.

What offline marketing works for an assisted living home?

Building referral relationships with discharge planners, home health and hospice agencies, and elder law attorneys, and other professionals that work with older adults can help connect your RCFE with families looking for care.. Small community event can also introduce your home to local families and professionals. These strategies typically require an investment of time and relationship-building rather than a large advertising budget.

Get Your RCFE Team Certified and Ready to Grow

Strong marketing only works if your facility is ready to deliver on what you promise. Assisted Living Education has helped thousands of California operators get licensed, certified, and trained.

If you are opening a new facility, start with our RCFE Administrator Certification initial class, which covers the state-required 80-hour course. Need help navigating the licensing process? Our RCFE license application service provides comprehensive application support tailored to your specific needs tailored to  your needs before you apply.

Already certified? Administrators must complete 40 hours of continuing education every two years to keep their certificate current. We offer flexible online and live Zoom options so you can renew without stepping away from your residents.

We also provide other caregiver training and staff classes that meet Title 22 requirements. You can always contact us with questions about your certification needs. We want to help you provide quality care to every resident who walks through your door.

Supporting Mental Health in Senior Living: What Administrators Need to Know

Key Takeaways for Administrators

Mental health in senior living isn’t just about clinical diagnoses—aging triggers like loss of independence, isolation, and bereavement often cause significant mental decline in residents. As an RCFE Administrator, it’s your responsibility to oversee total resident well-being through proactive assessments, tailored care plans, and staff training. Assisted Living Education prepares you for this role with California DSS-approved initial certification and continuing education courses focused on behavioral health, dementia, and person-centered care. 

Mental illness awareness goes far beyond clinical diagnoses like depression, anxiety, or bipolar disorder. In senior care, mental health exists on a broad spectrum. An elderly resident doesn’t need a diagnosed mental illness to experience a severe, quality-of-life-altering decline in mental well-being.

As an Assisted Living or Residential Care Facility for the Elderly (RCFE) Administrator, recognizing these subtle declines—and knowing how to intervene—is critical to providing exceptional, compliant, and compassionate care.

The Hidden Mental Health Decline in Aging Adults

Aging brings profound lifestyle transformations. Even residents with no prior history of mental illness can experience mental and emotional deterioration due to common late-life triggers:

  • Loss of Independence: Transitioning from an independent lifestyle to assisted living often triggers grief, loss of control, and loss of identity.
  • Social Isolation & Loneliness: Moving away from family, friends, and familiar neighborhoods can lead to withdrawal and emotional apathy.
  • Cognitive Changes & Chronic Illness: Physical pain, reduced mobility, sensory loss (hearing/vision), and early cognitive decline can cause frustration, helplessness, and agitation.
  • Loss of Loved Ones: Bereavement becomes more frequent, compounding feelings of sadness and existential distress.

Left unchecked, these non-clinical emotional struggles can manifest as physical decline, weight loss, refusal to take medications, and accelerated cognitive impairment.

Your Responsibilities as an Assisted Living Administrator

As an Administrator, state regulations and moral obligations require you to oversee total resident well-being—which includes emotional and mental wellness. Key administrative responsibilities include:

  1. Conducting Comprehensive Needs Assessments: Identifying emotional and behavioral patterns during pre-admission appraisals and ongoing re-assessments.
  2. Developing Person-Centered Care Plans: Ensuring service plans incorporate social engagement, behavioral support, and activities tailored to emotional needs.
  3. Staff Training & Supervision: Training direct care staff to recognize subtle warning signs of emotional distress, social withdrawal, or mood shifts.
  4. Environment & Activity Design: Fostering a community environment that promotes purpose, social connection, and daily structure.
  5. Managing Care Transitions: Coordinating timely referrals with healthcare providers, mental health professionals, or hospice services when care needs exceed the facility’s scope.

How Assisted Living Education Prepares You to Lead

Meeting the mental health needs of elderly residents requires practical, compliant education. Assisted Living Education integrates critical mental health and behavioral care principles throughout its curriculum:

1. Initial 80-Hour RCFE Administrator Certification Training Program (ICTP)

California DSS-approved 80-hour initial training program covers core regulatory and care modules, equipping new Administrators with essential tools:

  • Recognizing psycho-social needs and age-related behavioral changes.
  • Managing care plans for residents dealing with dementia, Alzheimer’s, and memory loss.
  • Implementing Title 22 regulations surrounding resident rights, dignity, and specialized care.

2. Continuing Education Units (CEUs)

To maintain certification, Administrators complete 40 hours of continuing education every two years. Our live and online CEU courses dive deeper into mental health topics:

  • Specialized dementia care and managing challenging behaviors.
  • Identifying depression vs. cognitive impairment in older adults.
  • De-escalation techniques, staff communication strategies, and trauma-informed care.

Prioritize Mental Health in Your RCFE Today

Promoting mental health awareness in assisted living starts with informed leadership. Equipping yourself and your care staff with proper training creates a safe, vibrant community where residents feel seen, supported, and valued.

Ready to start or renew your California RCFE Administrator certification? Explore our upcoming RCFE Initial Administrator Classes and Continuing Education (CEU) Packages to gain the skills needed for high-quality resident care.

Staff Checklist: Spotting Non-Clinical Mental Health Decline in Residents

Share this quick-reference observation checklist with direct care staff to catch emotional and mental health changes early:

Observation AreaWarning Signs to Watch ForRecommended Immediate Action 
Social & Activity EngagementWithdrawing from favorite social activities or mealsStaying in bedroom longer than usualAvoiding interaction with staff or peersNotify Administrator/Resident Care Coordinator; offer gentle 1-on-1 engagement in room.
Daily Living & Personal CareUnexplained neglect in personal hygiene or groomingRefusing meals, snacks, or hydrationsRefusing or repeatedly skipping medicationsDocument in resident log; report appetite/medication refusal to Administrator immediately.
Mood & Behavioral ShiftsUncharacteristic irritability, tearfulness, or angerExpressing feelings of being a burden or uselessnessIncreased anxiety during routine daily transitionsProvide immediate calm reassurance; log specific behavioral triggers and times.
Physical & Cognitive SignalsIncreased somatic complaints (pains/aches with no physical cause)Noticeable changes in sleep patterns (insomnia or hypersomnia)Sudden onset of apathy or confusionAssess for physical issues (UTI, dehydration, pain); schedule medical/assessment review.

Senior Mental Health & RCFE Compliance: Frequently Asked Questions

Can senior living residents experience mental health decline without a diagnosed mental illness?

Yes. Triggers like moving away from family, loss of independence, bereavement, and chronic physical ailments frequently cause non-clinical emotional decline, including apathy, anxiety, and social withdrawal.

What are an RCFE Administrator’s responsibilities regarding resident mental health?

Administrators must conduct thorough pre-admission appraisals and ongoing re-assessments, build person-centered care plans with social components, train direct-care staff to identify warning signs, and arrange appropriate care transitions when needed.

How does Assisted Living Education cover mental health in its curriculum?

Assisted Living Education incorporates mental health care into both its California DSS-approved 80-Hour Initial Administrator Certification (ICTP) and Continuing Education Units (CEUs), covering topics such as Title 22 compliance, dementia care, depression identification, and trauma-informed communication.

How often must RCFE Administrators complete continuing education in California?

California RCFE Administrators must complete 40 hours of approved continuing education every two years to maintain their certification.

Prioritize Mental Health in Your RCFE Today

Promoting mental health awareness in senior living begins with informed, proactive leadership. By equipping yourself and your direct-care staff with proper training, you build a safe, compliant, and vibrant community where residents feel valued and supported.

Ready to fulfill your California RCFE Administrator certification or CEU requirements?

Explore upcoming RCFE Initial Administrator Certification Classes and Continuing Education (CEU) Packages at Assisted Living Education today.

RCFE Profit Margins in California: 2026 Revenue & Cost Breakdown

Last reviewed: September 2026

Owning a Residential Care Facility for the Elderly (RCFE) in California can be rewarding, but it is not a passive-income business. A successful RCFE requires safe, high-quality resident care, careful staffing, regulatory compliance, effective marketing, and disciplined financial management.

The question is not simply, “How much profit does an RCFE make?” The more useful question is:

Can this specific RCFE generate enough revenue at realistic occupancy and pricing levels to cover payroll, property costs, insurance, food, utilities, compliance, marketing, debt service, reserves, and an appropriate return to the owner?

There is no universal RCFE profit margin. A six-bed residential care home, a 16-bed RCFE, and a larger 49-bed community can have very different economics because of their location, care needs, property costs, staffing model, financing, resident mix, and operational performance.

California’s aging population supports long-term demand for residential care, but demand is not evenly distributed. Each prospective operator should evaluate local population growth, household affordability, competing licensed beds, referral sources, caregiver availability, and local property economics before opening, buying, or expanding an RCFE.

If you are considering starting a facility, review these 10 steps to open an RCFE in California along with this profitability guide.

How Profitable Is an RCFE in California?

An RCFE can be profitable when it maintains stable occupancy, charges rates that reflect local market conditions and the actual level of resident care required, controls expenses responsibly, and consistently meets California’s licensing and care standards.

However, gross revenue is not owner profit. Gross revenue is the money collected from resident charges. Owner cash flow is what remains after operating expenses, rent or mortgage payments, debt service, taxes, insurance, owner compensation, repairs, and capital reserves.

For planning purposes, do not rely on a single “average RCFE profit” statistic. Build a facility-specific financial model using your own licensed capacity, expected occupancy, local pricing, staffing plan, property costs, and financing assumptions.

The RCFE revenue formula

A practical starting point is:

Annual Resident Revenue = Licensed  Beds x Average Occupancy x Average Monthly Revenue per Occupied Bed x 12

“Average monthly revenue per occupied bed” should reflect actual collected revenue—not just a published rate card. Include base rent, care-level charges, recurring fees, concessions, vacancies, move-in timing, and the actual mix of resident needs.

Example: 16-bed RCFE revenue

A 16-bed RCFE at 88% average occupancy with $6,500 in average monthly revenue per occupied bed would generate approximately:

16 x 0.88 x $6,500 x 12 = $1,098,240

That is approximately $1.1 million in annual resident-service revenue before expenses.

For context, the national median monthly cost for an assisted-living community was $6,200 in the 2025 CareScout Cost of Care Survey. California rates are generally higher; statewide consumer-cost benchmarks commonly place assisted living at roughly $7,000 per month. Actual rates vary materially by city, room type, care needs, amenities, and payer mix.

Illustrative RCFE revenue scenarios

These examples are for planning purposes only. They are not profit guarantees, statewide averages, or a substitute for a facility-specific pro forma.

Facility exampleLicensed bedsAverage occupancyAverage monthly revenue per occupied bedEstimated annual gross resident revenue
Small RCFE home690%$5,500$356,400
Higher-acuity six-bed home695%$7,500$513,000
Small-to-mid-size RCFE1688%$6,500$1,098,240
Premium 16-bed RCFE1692%$8,500$1,501,440
Larger RCFE community3090%$7,000$2,268,000
Larger RCFE community4990%$7,000$3,704,400

The key lesson is that bed count does not predict owner profit on its own. A high-occupancy six-bed home with reasonable property costs and a stable staffing model may outperform a larger facility with costly debt, weak occupancy, underpriced care, or high turnover.

The Key Profit Measures Every RCFE Owner Should Understand

When someone uses the term “profit,” they may be referring to several different financial measures. Understanding the distinction is essential before comparing facilities, evaluating a purchase, or deciding whether to open an RCFE.

Financial measureWhat it meansWhy it matters
Gross revenueResident base rates, care-level charges, recurring fees, respite revenue, and other income before expensesShows the facility’s revenue capacity
Operating expensesPayroll, food, insurance, utilities, maintenance, supplies, training, marketing, administration, and compliance costsShows what it costs to run the care operation
Net operating income (NOI)Revenue remaining after operating expenses, generally before debt service, income taxes, depreciation, and certain owner-level expensesHelps evaluate operating performance and property economics
EBITDAEarnings before interest, taxes, depreciation, and amortizationOften used in larger senior-living business analysis; definitions can vary
Owner cash flowMoney remaining after debt payments, rent, reserves, taxes, owner compensation, and other owner-level obligationsClosest to what many prospective owners mean by “take-home profit”

A facility can have strong gross revenue and a respectable NOI margin but still generate limited owner cash flow if rent, mortgage payments, acquisition debt, major repairs, owner compensation, or capital-reserve needs are high.

Typical RCFE Margin and Cost Ranges

There is no universal California RCFE margin benchmark that applies to every facility. The following are illustrative planning ranges. Actual results can differ significantly based on location, capacity, resident acuity, labor needs, real-estate ownership, debt, operational quality, and occupancy.

Margin or expense categoryIllustrative planning rangeImportant context
Average occupancy80%–95%A small RCFE can be materially affected by just one vacant bed
Payroll and benefits35%–55% of revenueCan be higher with high acuity, dementia care, overtime, awake-night coverage, agency staffing, or turnover
Food and resident supplies5%–10% of revenueVaries by meal program, resident needs, purchasing controls, and inflation
Rent, mortgage, and property expenses10%–30%+ of revenueOften the largest difference between owner-operated homes, leased facilities, and newly financed purchases
Insurance, utilities, repairs, maintenance, and technology7%–15% of revenueCalifornia insurance and property costs can materially affect results
Marketing, sales, administration, training, and compliance5%–12% of revenueFrequently under-budgeted by first-time operators
NOI or operating margin15%–35%Depends on stabilized occupancy, labor control, rates, property costs, and care mix
Owner cash flow after debt and reserves0%–20%+Can be negative during startup, major repair periods, or low occupancy

A higher margin is not automatically better if it results from understaffing, poor training, inadequate maintenance, or services that do not meet resident needs. Sustainable profitability depends on quality, compliance, and retention—not simply cost cutting.

Sample 16-Bed RCFE Financial Model

The following example shows how a 16-bed RCFE might look on paper. It is illustrative only and should not be used as a prediction of financial performance.

Revenue assumptions

Revenue assumptionAmount
Licensed beds16
Average occupancy88%
Average occupied beds14.08
Average realized monthly revenue per occupied bed$6,500
Annual gross resident revenue$1,098,240

Illustrative operating-expense breakdown

Expense categoryAnnual expensePercent of revenue
Payroll, payroll taxes, benefits, overtime, and coverage$494,20845.0%
Rent or property operating costs$164,73615.0%
Food and resident supplies$76,8777.0%
Insurance, utilities, repairs, and maintenance$98,8429.0%
Marketing, sales, administration, and technology$65,8946.0%
Training, licensing, professional services, and contingency$32,9473.0%
Total operating expenses$933,50485.0%
Estimated NOI$164,73615.0%

In this scenario, the RCFE generates roughly $164,736 in NOI before debt service, income taxes, depreciation, owner compensation, and capital-replacement reserves.

If annual debt service, owner compensation, and capital reserves total $125,000, the estimated remaining owner cash flow would be approximately:

$164,736 − $125,000 = $39,736

That is about 3.6% of gross revenue. This is why gross revenue should never be confused with owner profit.

Sample Six-Bed RCFE Financial Model

A six-bed RCFE can be an attractive owner-operator model, but it is often highly sensitive to vacancy. One open bed represents 16.7% of the home’s licensed capacity.

Revenue assumptions

Revenue assumptionAmount
Licensed beds6
Average occupancy92%
Average occupied beds5.52
Average realized monthly revenue per occupied bed$7,000
Annual gross resident revenue$463,680

Illustrative operating-expense breakdown

Expense categoryAnnual expensePercent of revenue
Payroll, relief coverage, payroll taxes, and benefits$199,38243.0%
Mortgage, rent, property taxes, and property expenses$102,01022.0%
Food and resident supplies$32,4587.0%
Insurance, utilities, repairs, and maintenance$41,7319.0%
Marketing, technology, training, and administration$27,8216.0%
Licensing, professional services, and reserves$18,5474.0%
Total operating expenses$421,94991.0%
Estimated NOI$41,7319.0%

In this scenario, the six-bed home produces about $41,731 in NOI before owner compensation, taxes, major capital repairs, and any additional debt not included in the property-cost line.

If one bed remains vacant for six months at $7,000 per month, the home loses:

$7,000 x 6 = $42,000

in gross revenue. That one vacancy could erase most or all of the projected annual NOI.

What Has the Greatest Impact on RCFE Profit Margins?

1. Occupancy

Occupancy is among the most important financial drivers for any RCFE. Fixed costs such as rent, mortgage payments, insurance, utilities, and many staffing costs continue whether every bed is filled or not.

For a 16-bed RCFE with $6,500 in average realized monthly revenue per occupied bed, the annual revenue impact of occupancy can look like this:

Average occupancyEstimated annual resident revenue
75%$936,000
80%$998,400
85%$1,060,800
88%$1,098,240
90%$1,123,200
95%$1,185,600

Moving from 80% to 90% occupancy adds approximately $124,800 in annual revenue before incremental resident-care costs.

2. Monthly revenue per occupied bed

Care needs vary from resident to resident. A facility that charges only a flat room-and-board rate may become unprofitable if residents require substantial assistance, medication support, supervision, transfers, or dementia-related care.

For a 16-bed RCFE at 88% occupancy, a $500 increase in average monthly realized revenue per occupied bed changes annual revenue by:

16 x 0.88 x $500 x 12 = $84,480

This does not mean an RCFE should automatically raise rates. It means owners should regularly evaluate whether their care-level pricing accurately reflects resident needs, staffing time, market conditions, and the services included in the resident agreement.

3. Staffing and labor management

Payroll is often the largest controllable operating expense. Staffing costs can rise quickly due to resident acuity, dementia care needs, medication workload, falls, mobility assistance, two-person transfers, awake-night coverage, overtime, turnover, sick time, and agency staffing.

California RCFE regulations require sufficient staff to provide care and supervision needed to meet resident needs. Staffing plans should be based on resident acuity and operational reality—not a simple headcount ratio.

4. Real estate, rent, and debt

Two RCFEs with similar occupancy and resident rates can have very different owner returns when one property is owned free and clear, another is leased at current rates, and another has high acquisition debt or major deferred maintenance.

Your model should account for:

  • Mortgage or rent payments
  • Property taxes
  • HOA fees where applicable
  • Maintenance and repairs
  • Accessibility upgrades
  • Fire and life-safety improvements
  • Furnishing replacement
  • Roof, HVAC, plumbing, and appliance reserves
  • Insurance premiums and deductibles

5. Resident acuity and care mix

Higher-acuity residents can support higher rates when pricing is structured properly. They can also require more staff time, training, documentation, supervision, and coordination with outside providers.

Memory care or dementia-focused care may support higher revenue, but it can also involve increased safety planning, staffing, family communication, and operational complexity. More revenue does not automatically mean more profit.

6. Vacancy, turnover, and move-in speed

Vacancy is expensive. Operators should track the time from inquiry to tour, tour to deposit, deposit to move-in, move-out to bed availability, and bed availability to move-in.

A strong process for responding to families, scheduling tours, following up, and maintaining referral relationships can reduce vacant-bed days and improve revenue stability.

California RCFE Costs That Affect Profitability

California RCFEs are licensed through the California Department of Social Services, Community Care Licensing Division. Compliance costs should be included in the operating budget, not treated as occasional surprises.

Potential costs include:

  • RCFE application and annual licensing fees
  • Administrator certification and renewal
  • Staff orientation, training, and continuing education
  • Criminal-background clearances and onboarding
  • Fire clearance, safety upgrades, and inspections
  • Property renovation or accessibility improvements
  • General liability, workers’ compensation, property, auto, and other insurance
  • Food, cleaning, laundry, utilities, and resident-care supplies
  • Medical-record, medication-documentation, or care-management systems
  • Legal, accounting, HR, payroll, and compliance support
  • Website, CRM, local SEO, reputation management, and advertising
  • Working capital during startup and occupancy ramp-up
  • Capital reserves for repair, replacement, and unexpected expenses

California RCFE rules require applicants to submit a financial plan of operation that demonstrates sufficient resources to meet the cost of providing resident care. Before opening, buying, or expanding a facility, develop a conservative cash-reserve plan that accounts for low occupancy, delayed move-ins, staff turnover, higher insurance costs, and repairs.

RCFE Licensing, Training, and Compliance

Operating an RCFE legally requires more than obtaining a facility license. It requires ongoing attention to resident rights, care plans, staffing, staff training, safety, documentation, incident response, emergency preparedness, and facility standards.

RCFE Administrator Certification

California RCFE Administrators must meet current Administrator certification requirements. The Initial Certification Training Program currently requires at least 80 hours of training. Administrator applicants must also meet examination and application requirements.

Administrator renewal requires continuing education during each two-year certification period. Before applying or enrolling in any training, verify the current requirements, fees, and deadlines directly with the California Department of Social Services because rules and schedules can change.

Learn more about RCFE Administrator certification training.

Staff training

Staff training is both a compliance and business-performance issue. Well-trained staff can improve resident care, reduce preventable incidents, support stronger family communication, improve documentation, and reduce turnover.

California regulations include initial and ongoing training expectations for RCFE staff, including staff who assist residents with personal activities of daily living. Build training time and training costs into the budget rather than treating them as an optional expense.

Explore RCFE staff training resources.

An RCFE is a nonmedical residential care setting. It provides housing, meals, care, supervision, and assistance with activities of daily living within the scope of California RCFE requirements.

An RCFE may coordinate with appropriately licensed providers for home health, hospice, therapy, skilled nursing, physician care, and other clinical services when permitted and appropriate. However, owners should not assume that an RCFE license alone allows the facility to directly provide skilled nursing, medical, or rehabilitation services.

Before advertising, staffing for, billing for, or directly providing specialized services, obtain qualified California legal, licensing, and clinical guidance.

Differentiating services that may support occupancy

Depending on the facility’s policies, staffing, resident needs, outside-provider relationships, and applicable requirements, an RCFE may differentiate itself through:

  • Dementia-care and memory-support programming
  • Enhanced family communication and care updates
  • Medication-management processes
  • Transportation coordination
  • Respite-care availability
  • Culturally responsive food, activities, and communication
  • Bilingual staffing or family support
  • Wellness, activity, and social-engagement programming
  • Technology-enabled documentation, safety, and communication systems
  • Coordination with home-health, hospice, therapy, and physician providers

Technology can improve workflows, documentation, resident engagement, and family communication. It does not replace required supervision, qualified staff, training, safety procedures, or care responsibilities.

How RCFE Operators Can Improve Margin Without Compromising Care

The safest way to improve profitability is not simply reducing expenses. Sustainable margin improvement comes from better occupancy, clearer pricing, resident-fit discipline, staffing efficiency, quality, and operational consistency.

OpportunityPotential financial benefitImportant caution
Improve occupancyGenerates more revenue from existing licensed capacityDo not accept residents whose needs exceed the facility’s capabilities
Update care-level assessmentsBetter aligns revenue with the true cost of careUse transparent, compliant resident agreements and reassessment processes
Reduce vacant-bed daysImproves revenue stabilityRequires fast lead response, tours, follow-up, and referral relationships
Improve staff retentionReduces overtime, recruiting, onboarding, and retraining costsDo not reduce training, fair compensation, or safe coverage
Strengthen referral relationshipsProduces more qualified move-insReferrals must be ethical and compliant
Improve purchasing controlsReduces food and supply wasteDo not compromise nutrition, sanitation, or resident preferences
Prevent deferred maintenanceReduces disruptive emergency repairsMaintain reserves for major repairs and replacement
Use technology carefullyImproves documentation and workflow consistencyTechnology does not replace resident care or supervision

Marketing and Referral Strategies That Support RCFE Occupancy

Families often begin their assisted-living or RCFE search online, compare reviews, talk with healthcare professionals, and contact multiple communities before scheduling a tour.

A strong occupancy strategy requires both consumer-facing marketing and professional referral development.

Effective RCFE marketing channels

  • Google Business Profile optimization
  • Local SEO for city, neighborhood, RCFE, assisted living, memory care, and dementia-care searches
  • A mobile-friendly website with clear calls to action
  • Accurate photography, videos, and virtual tours
  • Family testimonials and review-management processes
  • Paid local search campaigns when appropriate
  • Relationships with hospitals, skilled nursing facilities, home-health agencies, hospice providers, physicians, elder-law attorneys, and geriatric-care managers
  • Community education events and family resources
  • Social content that shows activities, meals, staff recognition, culture, and family communication
  • CRM tracking for inquiries, tours, deposits, move-ins, and referral sources

Marketing metrics that matter

Do not evaluate marketing only by website traffic or total calls. Track:

  • Qualified inquiries
  • Speed to first response
  • Inquiry-to-tour conversion rate
  • Tour-to-deposit conversion rate
  • Deposit-to-move-in conversion rate
  • Cost per move-in
  • Average time to fill a vacancy
  • Occupancy by month
  • Lead source for each move-in
  • Referral-source contribution
  • Review rating, review volume, and review themes
  • Lost-lead reasons

Strong marketing supports financial performance only when the facility can deliver an excellent tour experience, communicate its care capabilities clearly, respond promptly, and follow up consistently with families.

Is an RCFE a Profitable Business in California?

An RCFE can be a profitable business in California, but profitability is not determined by bed count or gross revenue alone.

The strongest operators build a location-specific financial model, maintain sustainable occupancy, price care appropriately, invest in staff training and retention, protect compliance, manage property and labor costs carefully, and provide care that earns family trust and referral relationships.

Before opening, buying, or expanding an RCFE, model revenue at several occupancy levels, including 75%, 80%, 85%, 90%, and 95%. Include payroll, rent or mortgage payments, insurance, food, utilities, maintenance, licensing, marketing, working capital, debt service, taxes, and a capital-replacement reserve.

A financially successful RCFE is not simply full. It is safely staffed, appropriately priced, compliant, operationally disciplined, and positioned to provide reliable, high-quality care.

California RCFE Profit Margin Questions Answered

What is a good RCFE profit margin in California?

There is no universal RCFE profit margin. A financially healthy facility should generate a positive operating margin after payroll, food, insurance, utilities, maintenance, marketing, training, and administration. Owner cash flow will generally be lower after rent or mortgage payments, debt service, taxes, owner compensation, capital reserves, and major repairs.

How much revenue can a six-bed RCFE generate in California?

Revenue depends on occupancy and average realized monthly revenue per occupied bed. For example, a six-bed RCFE at 92% occupancy with $7,000 in average monthly revenue per occupied bed would generate approximately $463,680 in annual gross resident revenue before expenses.

What occupancy rate does an RCFE need to break even?

Every RCFE has a different break-even occupancy rate. It depends on local rates, staffing costs, rent or mortgage payments, debt, insurance, resident acuity, food, utilities, and other overhead. Calculate break-even occupancy using a facility-specific pro forma and test multiple scenarios before opening or acquiring a facility.

What are the biggest operating expenses for an RCFE?

The largest costs commonly include payroll and benefits, rent or mortgage payments, food and supplies, insurance, utilities, maintenance, staffing coverage, training, administration, compliance, and marketing.

Does memory care have higher RCFE profit margins?

Memory care may support higher rates because residents may need more supervision, dementia-focused programming, and specialized support. However, it can also increase staffing, training, safety, documentation, family communication, and operational costs. Higher revenue does not automatically produce higher profit.

Can an RCFE provide physical therapy or rehabilitation services?

An RCFE is a nonmedical residential care setting. It may coordinate with properly licensed outside providers for therapy, home health, hospice, skilled nursing, physician care, and other clinical services when appropriate. Obtain qualified California legal, licensing, and clinical guidance before marketing or directly providing medical or rehabilitation services.

How do you calculate RCFE revenue?

Use this formula:

Licensed Beds x Average Occupancy x Average Monthly Revenue per Occupied Bed x 12

Then subtract operating expenses, rent or mortgage, debt service, owner compensation, capital reserves, taxes, and other owner-level costs to estimate owner cash flow.

Is owning an RCFE passive income?

No. An RCFE is an active care operation. It requires responsible management, regulatory compliance, staff training, resident-care oversight, family communication, property maintenance, occupancy management, and ongoing response to resident and staff needs.

How can an RCFE improve occupancy?

An RCFE can improve occupancy by strengthening its Google Business Profile, local SEO, reviews, referral relationships, speed to lead response, tour process, follow-up process, and ability to clearly communicate care capabilities, pricing, location, and resident experience.

What should an RCFE business plan include?

An RCFE business plan should include a local market analysis, licensing roadmap, facility plan, staffing model, pricing strategy, care model, marketing and referral strategy, startup budget, operating budget, occupancy forecast, cash-reserve plan, financial projections, and risk analysis.

Get Assisted Living Education Classes and Support

Get the training and support you need to run a successful RCFE. Our team of industry experts and educators will show you  how to meet all RCFE licensing requirements, RCFE Administrator Certification and RCFE continuing education online (RCFE CEU live classes) for your team. Our instructors have years of industry experience that will give you an edge in this growing and highly regulated industry. We are a DSS approved vendor as well as an approved vendor for BRN.

Creating a Culture of Healthy Aging in Your RCFE: A Lead Administrator’s Guide

As the senior living market matures, there is a tremendous shift in care. Not only do today’s seniors demand safety but more importantly a vibrant community that will offer them dignity and purpose, as well as a sense of wholeness.

Establishing a culture of healthy aging in an RCFE (Residential Care Facility for the Elderly) does not stop at fulfilling the obligations of Title 22 or providing good meals; rather it necessitates a change in mindset towards care.

What Does a Healthy Aging Culture Look Like in Assisted Living?

Healthy aging includes physical well-being, mental activity, emotional well-being, and social connections. In a community that has a vibrant culture of health, there are some specific markers that emerge:

  • Empowered Residents: Individuals are encouraged to maintain independence in their Activities of Daily Living (ADLs) whenever safely possible.
  • Trained & Compassionate Staff: Caregivers possess a deep understanding of dementia dynamics, infection control, and person-centered care.
  • Purposeful Programming: Activities are structured not just to pass time, but to stimulate memory, mobility, and social connection.
  • Proactive Health Monitoring: Early identification of condition changes prevents unnecessary hospitalizations.

The creation of such an environment will call for management teams, nurses, and caregivers to be well-educated, skilled, and certified by the state.

Key Pillars to Implement Healthy Aging in Your Community

1. Person-Centered Care Plans

Every resident brings a unique history. Facilities should move beyond standard care plans by incorporating personal preferences, past hobbies, and individual health goals into daily routines.

2. Comprehensive Dementia & Memory Support

With a growing population of residents experiencing cognitive decline, staff members must be equipped with evidence-based strategies for managing challenging behaviors, supporting dignity, and facilitating therapeutic dining experiences.

3. Continuous Staff Education & Compliance

Care quality directly reflects staff training quality. Keeping teams updated on California Department of Social Services (CDSS) and Community Care Licensing (CCL) regulations ensures both compliance and top-tier resident safety.

Elevate Staff & Leadership with Assisted Living Education

Creating a Culture of Health begins with state-of-the-art training. Assisted Living Education (ALE) provides state-approved training classes that are delivered by seasoned Administrators and instructors who are not only knowledgeable but experienced..

Whether you’re preparing to become a certified Administrator, renewing your license, or completing training for direct care providers, our online courses and livestream classes make it easy to learn on your schedule. 

Assisted Living Education Flagship Programs & RCFE Courses

1. Initial Certification

  • RCFE Administrator Certification Training
    • Format: 80 total hours (6 days of live Zoom instruction + 20 online self-study hours).
    • Details: This mandatory state-approved program covers Title 22 regulations, resident care, business operations, and medication management. Enrollment includes digital course materials and access to a 200-question RCFE Test Preparation course to prepare students for the California state exam at competitive rates.

2. Continuing Education & Recertification (CEUs)

California RCFE Administrators must complete 40 CEU hours every two years to maintain certification. ALE offers competitively priced packages to complete these requirements seamlessly:

  • RCFE CEU Class – 20 Live on Zoom + 20 Online
    • Format: 2 days of live Zoom classes (20 hours) paired with 20 hours of self-paced online CEUs.
    • Details: The ultimate renewal package fulfills all CDSS requirements, including mandatory hours in Dementia Care and DSS Laws & Regulations.
  • 20 Hour Live RCFE Administrator Classes
    • Format: 2-day live classes via Zoom (10 hours/day).
    • Details: Perfect for Administrators who need to complete mandatory live instruction hours in an interactive environment with peer networking opportunities.

3. Additional Training Options

Explore the complete catalog on the RCFE Training Classes Overview Page, which features competitive rate structures for:

  • 10-Hour Livestream Classes: Ideal single-day options for partial live credit.
  • 20-Hour Online CEU Package: Preselected self-paced courses accessible for 90 days.
  • DSS Required Staff Training Subscriptions: Turnkey caregiver, dementia, and medication training modules designed for teams of all sizes.

Operational Insights: Wellness Through Targeted Staff Training

In what ways does continuing education help cultivate a proactive wellness culture?

As leaders and caregivers undergo specialized training in subjects such as Infections and Diseases, Pain Management, and Common Diseases of Residents, their ability to recognize even subtle changes in a resident’s health improves significantly. Rather than waiting until a clinical clinical decline has occurred, staff can identify early changes in mobility, cognition, appetite, or other aspects of a resident’s well-being and respond promptly.

What special subject courses should be taught to better assist in memory care and aging?

Cultivating a culture of wellness requires going beyond mere custodial care. Classes such as Alzheimer’s Disease & Dementia, Dining, Dementia & Dignity, and Dementias Beyond Alzheimer’s provide caregivers with the tools they need  to manage difficult behaviors, promote healthy eating through specialized dining strategies, and protect residents’ autonomy and dignity at every stage  of dementia.

How does the need to take CEUs benefit both compliance and staff retention?

Compliance and operational efficiency are closely interconnected. By completing state-mandated training, such as DSS Laws, Regulations & Policies along with leadership courses like Creating a Successful Caregiving Team and Interview, Hire & Fire, Administrators can strengthen their leadership skills, reduce staff turnover, and maintain a stable, knowledgeable care team.

What is the most efficient way to train direct care staff while maintaining community activities?

Balancing mandatory staff training with the ongoing delivery of quality care can be challenging. Flexible online modules covering caregiver basics, medication policies, and dementia care allow caregivers to complete training in manageable segments  without leaving residents alone in this process.

Transform Your RCFE Facility Today

A culture of healthy aging is something that doesn’t just happen—it requires leadership, education, and process.

Develop your leaders in the field of assisted living and empower them to lead change using the best RCFE training available in California!

7 Actionable RCFE Revenue Growth Strategies (California Operator Insights)

Running a successful Residential Care Facility for the Elderly (RCFE) in California requires far more than providing quality senior care. With over 31,000 senior living communities nationwide serving approximately 2.1 million residents, maximizing RCFE revenue while maintaining exceptional service standards is critical to long-term operational sustainability.

At Assisted Living Education, our team has consulted with hundreds of RCFE facility owners across California, helping them navigate complex RCFE licensing, state regulations, and operational finance. As a leading RCFE educational training program in California, we have identified seven core strategies that drive revenue growth, optimize profit margins, and keep occupancy rates high for RCFE operators.

1. Optimize Pricing Strategy with Dynamic Level of Care (LOC) Structures

Strategic pricing forms the foundation of financial health for any RCFE. Many operators undervalue their services or rely strictly on flat room-and-board fees, leaving significant net income on the table. Research indicates that communities aligning sales, pricing models, and resident assessments can achieve up to a 20% increase in overall facility revenue.

Market Benchmarking and Value Positioning

Begin by conducting a localized market analysis of competitor pricing. Factor in your unique amenities, staff-to-resident ratios, specialized care programs, and geographic advantages. Prospective residents and their families prioritize high-quality care and safety over finding the lowest price point.

Navigating California’s 90-Day Rate Increase Regulations

For facilities operating at or near capacity, routine annual rate increases represent a direct path to margin expansion. Under California Health and Safety Code Section 1569.657, RCFEs must provide at least 90 days prior written notice before implementing rate increases for basic services.

Implementing a Points-Based Tiered Care Model

Instead of rigid pricing blocks, adopt a dynamic points-based Level of Care (LOC) pricing matrix. Assign point values tied to labor-minutes for direct care tasks—such as two-person transfers, daily incontinence management, medication administration, diabetic management, or nighttime checks. As a resident’s acuity increases, care charges adjust immediately, capturing earned revenue without violating state notice timelines.

2. Maximize RCFE Occupancy Through High-Intent Referral Channels

create a successful RCFE facility
Strategic marketing ideas will keep your RCFE growing.

Unoccupied beds generate zero revenue while maintaining fixed overhead costs. Maintaining high RCFE occupancy directly drives bottom-line profitability and overall return on investment (ROI).

Digital Marketing vs. Local Referral Networks

While online searches for senior living options have increased by 15% annually, digital marketing strategies yield vastly different results based on facility size:

  • Large Senior Communities (50+ beds): Benefit heavily from digital search engine optimization (SEO), virtual tours, pay-per-click advertising, and active social media channels.
  • Small to Mid-Sized RCFEs (e.g., 6-bed board & care): Achieve higher lead conversion rates and ROI by cultivating relationships with localized, professional referral channels.

Building Sustainable Referral Pipelines

Focus business development efforts on local healthcare ecosystems: hospital discharge planners, case managers, elder law attorneys, placement agencies, and local physician networks. Establishing strong relationships with healthcare providers creates a reliable flow of prospective residents.

3. Diversify RCFE Revenue Streams Beyond Room and Board

create diverse revenue streams
Assisting seniors with things like making beauty salon appointments and coordinating trips will add complementary revenue.

Top-performing RCFE operators look beyond basic room and board charges by introducing ancillary services and specialized sub-acuity programs that command premium private-pay rates.

High-Acuity Specialization and Hospice Waivers

Competing on basic care often triggers local price wars. By securing proper licensing waivers—such as high-acuity memory care, specialized wound care, or hospice waivers—your facility can serve complex resident populations. Because placement options for high-need seniors are limited, specialized facilities can charge premium rates.

Structured Respite Care and Short-Term Stays

Unoccupied rooms can be converted into immediate cash flow through structured respite care programs. Offering temporary stays (7 to 30 days) at a premium daily rate generates short-term revenue and serves as a low-friction pipeline for full-time permanent placements.

Third-Party Ancillary Partnerships

Offering boutique amenities—such as on-site salon services, physical therapy coordination, or specialized transportation—adds value for residents. To prevent staff overtime and liability risks, partner with vetted third-party vendors who pay facility placement fees or handle billing directly, keeping your direct-care staff focused on primary care tasks.

Leveraging Medi-Cal & CalAIM Funding Streams

For facilities managing mixed-income populations or private-pay to Medi-Cal transitions, explore funding opportunities available through CalAIM (California Advancing and Innovating Medi-Cal) and the Assisted Living Waiver (ALW) program. Leveraging Enhanced Care Management (ECM) and Community Supports helps cover care coordination expenses and home transition costs.

4. Leverage Technology for Operational Efficiency and Staff Cost Control

In California’s high-wage regulatory landscape, labor remains the single largest expense for RCFE operators. Technology investments streamline administration, lower overhead, and optimize care tracking.

Integrated Electronic Health Records (EHR) & eMAR

Implementing Electronic Health Records and Electronic Medication Administration Records (eMAR) reduces nursing documentation time, prevents costly medication errors, simplifies state regulatory compliance audits, and provides precise data for Level of Care billing.

Automated Billing, Accounting, and Safety Systems

Automating monthly invoicing and fee collection stabilizes cash flow and minimizes administrative overhead. Additionally, integrating modern resident safety monitoring technologies helps maintain resident safety standards while optimizing staff-to-resident scheduling ratios.

5. Maximize Resident Retention and Staff Satisfaction

Taking care of your residents will create long-term retention and satisfaction.

Resident retention is significantly more cost-effective than acquiring new residents. High turnover increases marketing expenditure, delays occupancy stabilization, and generates administrative overhead.

Comprehensive Wellness and Mental Health Engagement

Approximately half of senior living residents experience symptoms of depression. Implementing engaging wellness activities, cognitive exercises, and social interaction programs improves quality of life, reduces health complications, and extends average length of stay.

Investing in Direct-Care Staff Retention

Consistent, well-trained care staff foster trusting relationships with residents and their family members. Reducing caregiver turnover improves care consistency, elevates resident satisfaction, and prevents costly staffing agency fees and overtime spikes.

6. Strategic Market Positioning and Demographic Targeting

Before expanding operations or purchasing additional facilities, analyze local market demographics, local competitor capabilities, and unmet healthcare needs in your surrounding geographical area.

Developing Your Unique Selling Proposition (USP)

Differentiate your RCFE by tailoring your service model to specific, underserved market niches—such as specialized dementia care, culturally tailored dietary and lifestyle programs, or luxury boutique amenities. A strong USP justifies higher rates and reduces direct competition from surrounding standard facilities.

7. Structured Lead Management and Conversion Strategies

Consistently increasing RCFE occupancy requires systematic lead management and strong family engagement from initial contact to move-in day.

Tracking Key Sales Metrics

Use a centralized system to track inquiry sources, initial contact response times, scheduled tours, and tour-to-move-in conversion rates. Analyzing this data ensures marketing resources are allocated to the most profitable channels.

Streamlined Move-In Coordination Services

Simplifying the transition process for new residents and their families lowers move-in stress. Positive onboarding experiences lead to higher family satisfaction, online reviews, and professional word-of-mouth referrals.

Key Takeaways for California RCFE Administrators

Operational Focus AreaKey Revenue & Cost Control Strategy 
Pricing & Rate StructureImplement a dynamic, points-based Level of Care (LOC) system to capture care fee increases instantly without triggering the 90-day rate increase notice rule.
Occupancy OptimizationBuild direct healthcare referral pipelines (hospitals, case managers, placement agents) for small/mid RCFEs while deploying digital SEO/AEO for large facilities.
Revenue Stream DiversificationIncorporate high-acuity waivers (hospice, memory care), structured short-term respite programs, and explore CalAIM/ALW funding mechanisms.
Operational EfficiencyAdopt EHR/eMAR software to eliminate billing errors, automate administrative processes, and optimize caregiver labor costs.

Sustainable profitability in the RCFE industry requires a balance of financial discipline, regulatory compliance, and genuine resident care. By implementing these revenue growth strategies, California RCFE owners can build resilient, highly profitable senior care facilities.

7 Frequently Asked Questions on RCFE Growth

Does California’s 90-day rate notice rule apply to Level of Care (LOC) adjustments?

No. The 90-day notice applies only to basic room and board increases. Care fee adjustments based on changes in a resident’s care needs can take effect immediately.

How does a points-based Level of Care (LOC) model protect profit margins?

It ties caregiver labor minutes to specific dollar values. As resident acuity increases, care charges scale automatically, ensuring immediate compensation for higher labor costs.

What is the best referral pipeline for small-to-mid RCFEs?

Direct relationships with hospital discharge planners, placement agencies, case managers, and elder law attorneys yield much higher conversion rates than general digital ads.

How can RCFEs diversify revenue without inflating payroll?

Offer premium respite stays, secure high-acuity licensing waivers (memory care, hospice), or partner with third-party vendors for amenities rather than using in-house staff.

How does technology directly impact an RCFE’s bottom line?

eMAR and EHR platforms reduce documentation time, cut medication errors, streamline compliance audits, and provide exact data to justify LOC care charges.

Can California facilities leverage Medi-Cal programs to boost funding?

Yes. Participating in CalAIM (ECM/Community Supports) and the Assisted Living Waiver (ALW) helps cover care coordination and transition costs.

How does reducing caregiver turnover directly improve an RCFE’s net revenue?

Caregiver turnover creates significant expenses in recruiting, overtime backfill, and onboarding wages. Investing in staff retention protects net profit margins, prevents compliance violations, and maintains care consistency.

To elevate your operational knowledge and ensure your team stays fully compliant with California regulations, explore the comprehensive RCFE training classes and certification courses provided by Assisted Living Education.

How To Prepare for the RCFE Administrator Certificate Test

You’ve set an important career goal as an Administrator of a California assisted living facility, knowing the demand for excellent residential care facilities for the elderly is increasing in our state. In fact, the Public Policy Institute of California has determined a little more than 1 million Californians will require some help with their daily living activities by 2030.

To begin an RCFE Administrator career, you need to take the 80-hour RCFE Initial Certification Training Program (ICTP), required by the California Department of Social Services (CDSS). The class is divided into two requirements: 60 hours attending a live class and 20 hours completed online, at your own pace. Once you successfully complete this exciting step, you have 60 days to pass the state examination. You must achieve at least a 70% score to receive your Administrator certificate. The exam is 100 questions and open-book using Title 22 and the Health & Safety Code. 

Keep in mind: Passing the test is step one. Once you receive your passing notice, you have 30 days to submit your initial application (Form LIC 9214) and $140 state fee to the Administrator Certification Bureau (ACB). Missing this 30-day window voids your exam score.

If this two-hour test of 100 questions sends chills up your spine, don’t despair. We have some helpful strategies and proven study tips. Take each step, work hard on your RCFE classes and prepare for the test, and you can be on the way to your assisted living Administrator certification.

Note the Qualifications for an RCFE Administrator Position

Before digging into study strategies, it’s helpful to review the requisites for an assisted living Administrator. California assigns regulation of RCFEs to the Department of Social Services. The RCFE Administrator of a facility with one to 15 residents must meet these requirements:

  • Be at least 21 years old
  • Possess a high school diploma or GED
  • Pass a Criminal Record Clearance
  • Health screening and a negative TB test
  • First aid and CPR certification*

*Note: While CPR and First Aid certification are required to work on-site in an RCFE under Title 22, the state does not require proof of CPR to sit for the exam or submit your initial Administrator application.

Shortcut for NHAs: If you already hold a valid California Nursing Home Administrator (NHA) license, you are exempt from the 80-hour ICTP course and state exam. You only need to complete a 12-hour core program to apply.

To run a larger RCFE, the Administrator must complete these requirements plus attain one year of experience and 15 college credits to work with 16 to 49 residents. Three years of experience and two years of college qualify the Administrator to run a facility with 50 or more residents.

Begin Preparations With California RCFE Administrator Training

The required administrator certification training lays the foundation for everything needed to pass the certification test. Choose the vendor for all RCFE classes carefully. Talk to others who have taken the classes and make sure the content is clear, thorough, and helpful.

Start Early

Verify that you can begin the online training as soon as you register and start that portion of the course immediately. Set aside a regular time and quiet place to study and adhere to it. Post sticky notes around the house and utilize them to focus your attention on coursework rather than social media or Netflix.

Develop a Positive Mindset

This certification course differs from classes you had to take in school. You’ll actually use the materials you study here every day as you operate your RCFE and take care of your residents. For this reason, it is important to develop a positive mindset about the course material.

Relate Course Materials to Real Life

As you learn from your instructor, apply the information to real-life experiences. Even if you aren’t currently working in a care facility, for example, think about how the knowledge about the health and nutrition needs of the elderly applies to your grandparents or an elderly neighbor.

Take a FREE RCFE Administrator Practice Test!

As part of Assisted Living Education’s exhaustive RCFE Administrator certificate training, you’ll get free access to our 200-question RCFE Administrator practice test. This will be your most complete way of preparing for the actual test which you will now take with greater confidence.

As you move from course completion to test preparation, concentrate on the following strategies:

Review Your Materials in Sections

Your instructor conducted the Administrator certification training in sections, and this is a good way to review for the test. Develop a grid with a block for each day before the test, and cross out days unavailable for study. Write down your study plans for each day. If you don’t get to everything, reschedule the remainder for a future day.

Focus On Areas of Weakness

Inevitably, each trainee finds some areas of the course harder to master than others. Concentrate on subjects more difficult to understand or that give you problems on quizzes.

Consider a Formal RCFE Test Preparation Class

A test prep class gives you necessary information about what to expect on test day, as well as plenty of strategies to ensure you are ready. These practice tests for RCFE classes help you prepare and give you confidence. As mentioned previously, Assisted Living Education includes a free RCFE practice test as part of our online course training.

Review the Test Mechanics

Important facts about the test can help you get ready. For example, you have two hours or 120 minutes to answer 100 multiple-choice questions.

You will basically have one minute per question, so answer the ones you know first. Once you have completed the ones you know, go back and look up the ones you skipped. Remember, one minute goes fast. Once you have completed the exam, try not to overthink the answers. So many people have changed a correct answer to incorrect because they finished early and over thought the answers.

Understand the Stakes: Exam Fees and Limits

While you are mastering the test mechanics, it is just as important to understand the financial and regulatory stakes of exam day. When you are ready to schedule your test, you will navigate to the CDSS CCLD portal to submit a $100 non-refundable registration fee. Once your training is complete, a critical countdown begins: you have exactly 60 days and a maximum of three attempts to pass the exam. The state is incredibly strict about this three-strike rule. If you fall short on your third try, your progress is completely wiped clean, and state law requires you to start over from scratch. You will have to retake—and repay for—the entire 80-hour certification course. Keeping these stakes in mind is exactly why taking your time, utilizing practice exams, and walking into test day fully prepared is so vital to your success.

Acquaint Yourself With Allowed Materials

Since this is an open-book test with these materials, you don’t need to memorize them. We recommend learning the table of contents in Title 22 so you are familiar where to find an answer while testing. This will save you precious time during the exam. Currently, the exam is being conducted online. You may have Title 22 and the Health and Safety codes open on your computer. You may also use the Title 22 copy from the course.

If DSS goes back to “in-person” testing, you may not take any materials into the exam with you. They will provide a copy of Title 22 and the Health and Safety codes, but you will return these after the exam.

2026 Testing Tip: Ensure your copy of Title 22 includes recent state updates! The exam heavily tests exact regulatory numbers, and recent CDSS updates—such as the mandatory use of person-first language in assessments and the new CARE inspection tool—are highly testable topics this year.

Take Multiple Practice RCFE Administration Tests

Whether you are giving a speech, playing an instrument, or taking a test, the most important step is practicing. Not only do practice tests help you learn, but they also pinpoint areas of weakness needing additional study.

You Got This!

Passing the California RCFE Administrator exam is necessary to become a certified RCFE Administrator, and with determination and a good plan, you too can attain the 70% score to receive your certification. Start your test preparations today, and you can be on your way to a meaningful career. And if you need help, don’t hesitate to reach out to us at Assisted Living Education.

Questions People Also Ask On RCFE Certification

What is an RCFE Administrator certification?

RCFE stands for Residential Care Facility for the Elderly. An RCFE certification is a credential that demonstrates an individual’s training and competence in providing care for the elderly in a residential setting.

How do I obtain an RCFE Administrator certification?

To obtain an RCFE Administrator certification, you must complete a state-approved training program. The program typically covers topics such as resident care, medication management, and facility regulations. After completing the training, you will need to pass an exam to receive your certification.

What are the eligibility requirements for RCFE certification training?

Eligibility requirements for RCFE certification training vary by state but generally include a minimum age, a high school diploma or equivalent, and a clean criminal background check. Some states may also have specific experience or education prerequisites.

How long does RCFE certification training take?

The duration of RCFE certification training includes 80 hours; 60 hours is live online with an instructor and 20 hours of self-study done online.

Can I take RCFE certification training online?

Yes, many RCFE certification training programs offer online courses. However, it’s crucial to ensure that the online program is state-approved to meet certification requirements.

What topics are covered in RCFE certification training?

RCFE certification training covers a range of topics, including resident rights, dementia care, nutrition, emergency procedures, and legal and ethical considerations in elder care.

Is RCFE certification the same nationwide?

While the basic principles of RCFE certification are similar across the United States, each state has its own set of regulations and requirements. It’s essential to be familiar with the specific regulations of the state in which you plan to work.

Can I work in an RCFE without certification?

In most states, RCFE certification is required to work in a Residential Care Facility for the Elderly as an Administrator. Caregivers must complete specific training in California to ensure they have the necessary knowledge and skills to provide quality care to residents.

How often do I need to renew my RCFE certification?

RCFE certification must be renewed every 2 years. You must complete 40 hours of Continuing Education Units (CEUs) during each 2-year cycle. State law mandates that these hours include specific core topics, including a minimum number of hours dedicated to dementia care training.

What career opportunities are available with RCFE certification?

With RCFE certification, individuals can pursue various careers in the field of elder care, such as becoming a residential care facility Administrator, caregiver, or working in a managerial role within an assisted living community.

Assisted Living Education is Here to Help You Get There

Passing the California RCFE Administrator exam is necessary to become a certified RCFE Administrator, and with determination and a good plan, you too can attain the 70% score to receive your certification. Start your test preparations today, and you can be on your way to a meaningful career.

Ready to take the next step? Explore our comprehensive RCFE training classes at Assisted Living Education. Recognized as the top choice for Administrator training in California, we are proud to be highly rated by our students on both Google and class review platforms. Whether you need the initial 80-hour certification course, test prep, or continuing education, our expert instructors are here to ensure you succeed and feel fully prepared for exam day.

RCFE Administrator Exam Prep Course Overview

This video provides a helpful breakdown of the core topics covered in an online, self-paced test preparation course to help you pass the certification exam on your first attempt.

RCFE Staffing Requirements Overview – A Quick Reference

In California, one option for seniors 60 years or older requiring long term care is a “social model” that provides room, meals, personal care assistance, supervision, observation, housekeeping and planned activities. A Residential Care Facility for the Elderly (RCFE) can care for one or more persons and must be licensed by the State of California to provide care services.

RCFEs operate as a bridge for those who require some level of assistance that prevents them from living on their own but who do not require 24-hour medical care, service, or supervision.

RCFE’s vary in size but there are basically two models: 16+ residents or 1-15 residents. The 16+ are owned or operated by Sunrise, Brookdale and Atria to name a few. The 1-15 model is typically a home in a residential area and often called a “board and care”. Unlike nursing homes, RCFEs may have licensed professionals as personnel, but it is not required to do so.

RCFE Administrator Certification and Licensing

The Administrator is responsible for the care and supervision of residents, staff management, and adhering to regulations, policies and procedures. Regulations require the Administrator to complete an 80-hour certification course and pass a 100 question state examination with a score of 70% or better to receive a certificate.

The Administrator must complete 40 hours of continuing education units (CEUs) every two years. Fortunately, Assisted Living Education (ALE) is one of very few reputable vendors that provide RCFE Administrator certification classes. Additionally, the RCFE itself must be licensed by the California Department of Social Services (CDSS). The licensing process includes completing an RCFE license application and meeting CDSS licensing requirements. ALE offers assistance with your RCFE application and licensing. Once licensed, RCFEs are subject to ongoing monitoring and unannounced inspections by CDSS to ensure compliance with California laws and regulations.

RCFE Staff Requirements

California regulations require RCFE facilities to have sufficient staff at all times who are competent to provide the services necessary to meet residents’ needs. The required staffing level is based on factors such as the number of residents, their individual care needs, the services provided by the facility, and the physical layout of the facility. CDSS may require additional staff when necessary to adequately meet residents’ needs. 

California does not establish one universal caregiver-to-resident ratio that applies to every RCFE. Instead, staffing must be sufficient to meet the needs of the residents at all times. Facilities with 16 or more residents are subject to additional staffing provisions under Title 22. . 

The facility must also have appropriate Administrator coverage in accordance with California regulations, including a qualified designated substitute when the Administrator is absent. 

California regulations require the following:

  • Age requirements: Employees who provide direct care to the residents and employees who supervise employees must be 18 years or older. The Administrator must be 21 years or older.
  • Administrator education requirements: The Administrator must have a high school diploma or GED for 1-15 residents; 15 college units and one year of experience for 16-49 residents; 2 years of college and three years experience for a community with 50 or more residents.
  • Certifications: At least one staff member must be CPR certified and on the premises 24 hours per day. Any personnel who provide care to the residents must have first-aid certification.
  • Clearances: All personnel and some volunteers must have a Criminal Record Clearance before employment approval. All personnel must have a health screen and negative TB test.
  • Support personnel: Additional staff shall be employed as necessary to perform office work, cooking, house cleaning, laundering, and maintenance of buildings, equipment and grounds.

RCFE Staff Training Requirements

All personnel assisting residents with ADL’s must complete 20 hours of initial training prior to assisting a resident and an additional 20 hours of training within the first four weeks of employment.

The topics include: the aging process; personal care; physical limitation; ADL’s; resident rights; medication policies and procedures; psychosocial needs of the elderly; recognizing signs and symptoms of dementia; 12 hours of dementia training; postural supports; hospice care; restricted health conditions; LGBT; elder and dependent adult abuse reporting; theft and loss; disaster training; food service and safety; and care of a bedridden resident.

Staff also receive training on workplace health and safety topics, including universal precautions, Hepatitis B, bloodborne pathogens, personal protective equipment (PPE), and Safety Data Sheets (SDS), as required by applicable OSHA standards. 

All staff assisting residents with self-administration of medications must receive 10 hours of training for 1-15 residents and 24 hours of training for 16 or more residents.All communities must provide an additional 8 hours training each year.

ALE provides online training that allows employees to complete their coursework at their own pace. The following link will provide information about ALE’s training products for staff training.

RCFE Policies and Procedures

Once the facility is licensed, RCFEs are required to have a Plan of Operation that includes: policies and procedures for admissions; staffing plan, qualifications and duties; plan for training staff; organizational chart; sketches of the floorplan and the yard; policy for family visits and communication. ALE has created an assisted living policies and procedures manual.

Thank you for the essential care RCFE delivers to the aging community, and we hope the information provided in this article will help you continue to achieve that goal.

RCFE Staffing Frequently Asked Questions (FAQ)

What is the difference between ARF and RCFE?

An Adult Residential Facility (ARF) provides 24-hour non-medical care for adults ages 18-59 who need basic care, supervision, or personal care assistance. A Residential Care Facility for the Elderly (RCFE) provides non-medical care specifically to seniors 60 years or older who need assistance with activities of daily living (ADLs). Neither facility requires 24-hour medical or nursing care.

How many staff members are required at an RCFE in California?

California law requires RCFEs to have “sufficient staff at all times” to meet resident needs rather than mandating strict numerical ratios. Facilities with 1 to 15 residents typically staff two to three caregivers during the day and one at night, with Administrator coverage in accordance with California regulations, including a qualified designated substitute when the Administrator is absent.

Do RCFE staff members need to be licensed medical professionals?

No. Unlike nursing homes, RCFEs operate on a social model rather than a medical model. RCFEs may employ licensed healthcare professionals as personnel, but California regulations do not strictly require them to do so.

What are the training hours required for RCFE direct care staff?

Direct care staff assisting with ADLs must complete 40 total hours of initial training (20 hours prior to working with residents and 20 hours within the first 4 weeks). Staff assisting with self-administration of medication require 10 hours of training (for facilities with 1-15 residents) or 24 hours (for 16+ residents), plus 8 hours of continuing training each year.

What age must you be to work at an RCFE?

Employees who provide direct care or supervise other staff members must be at least 18 years old. Administrators must be at least 21 years old.

Elderly Heat Stroke Prevention: A Daily Checklist to Catch Dehydration Early

Elderly Heat Stroke Prevention: A Daily Checklist to Catch Dehydration Early

By the time an older adult tells you they are thirsty, the easiest window to intervene has usually already closed.

That one fact shapes everything that follows in heat illness prevention. Heat illness in older adults is rarely a dramatic collapse in the courtyard. It is a slow drift. It starts with a skipped glass of water on Tuesday, continues through a bedroom that never fully cooled overnight, and surfaces on Thursday afternoon as a resident who is suddenly confused and unsteady. Every stage of that drift was observable. Most of the stages were never written down.

For RCFE Administrators, direct care staff, and the home-visit volunteers who check on seniors aging in place, the challenge is not knowing that heat is dangerous. Everyone knows that. The challenge is that early dehydration in older adults is quiet, easy to mistake on something else and difficult to detect when caregivers rely on individual symptoms alone. 

This guide covers what California regulation actually requires, what the clinical research says about spotting dehydration (which surprises most caregivers), and a daily health-check checklist you can put into service before the next heat advisory hits your ZIP code.

Why Older Adults Reach Danger Before Anyone Notices

Aging does not weaken one heat defense. It weakens several at once, and they compound.

  • Thermoregulation declines. Older adults sweat less and dilate blood vessels less efficiently, so the body sheds less heat for every degree of exposure.
  • The body’s thirst response weakens. Many older adults don’t feel thirsty until they are already dehydrated, making it much easier to miss the early signs of fluid loss.
  • Total body water drops. Less fluid reserve means a smaller deficit produces a larger physiological effect.
  • Chronic conditions narrow the margin. Heart failure, chronic kidney disease, diabetes, and COPD all reduce tolerance for both heat and fluid loss.
  • Medications work against cooling. Diuretics, ACE inhibitors, beta blockers, anticholinergics, antipsychotics, and lithium each affect fluid balance, sweating, or cardiovascular response.
  • Cognitive and mobility limits block self-rescue. A resident with moderate dementia will not relocate to the cooled dining room on their own, and a resident who cannot lift a full pitcher will not refill their own glass.

The impact of these combined risk factors is reflected in the mortality data. Americans aged 85 and older carry the highest heat-related death rate of any age group, at roughly 2.13 deaths per 100,000 residents annually. A 2026 analysis in The Lancet Planetary Health that followed more than 73 million Medicare beneficiaries found that each additional heat wave was associated with an increase of 8.83 deaths per 10,000 person-years, measured across a full year rather than only the days immediately after the event. The harm does not end when the forecast cools off.

The CDC frames the underlying issue plainly: people aged 65 and over are less likely to sense and respond to changes in temperature. Which means the responsibility for noticing shifts falls entirely on the people around them.

What Title 22 Requires, and Where It Stops

California sets a floor for licensed facilities. Title 22, Section 87303(b) requires a comfortable temperature in all areas of an RCFE facility. Rooms that residents occupy must be heated to a minimum of 68 degrees Fahrenheit and cooled to a comfortable range between 78 and 85 degrees. In areas of extreme heat, the standard shifts to 30 degrees below the outside temperature.

Read that second half carefully. When it is 112 degrees outside in the Coachella Valley, the regulation is technically satisfied at 82 degrees indoors. For a frail 88-year-old on a loop diuretic, 82 degrees is not a safe resting temperature across a four-day heat event, and it is especially not safe overnight when the body normally gets its chance to recover. Compliance and safety are related targets. They are not the same target.

California Community Care Licensing has addressed the gap directly. Provider Information Notice 18-08-CCLD, issued to all community care licensed providers, directs licensees to review their facility emergency plan and confirm it includes the following:

  • Up-to-date emergency telephone numbers
  • Contingency plans for a failure of the facility air conditioning system
  • An evacuation plan in case residents need to be moved to a motel or other cooling centers
  • Information on local cooling centers
  • A process for reporting heat-related illnesses or deaths to the local licensing office

The same notice instructs providers to monitor residents taking medications that increase the likelihood of dehydration, and to obtain medical attention for a rapid strong pulse, delirium, or a body temperature above 102 degrees.

Here is what the regulation does not do. It does not tell you how often to check a resident during a heat advisory. It does not tell you what to look for. It does not tell you how to document any of it. That design work belongs to the administrator, and it is exactly the work that surveyors will ask about after an incident.

The Detection Problem Nobody Warns Caregivers About

Most caregiver training programs still teaches the skin pinch test, dry mouth, and thirst as the front line for spotting dehydration. The research says those signs do not work in this population.

A Cochrane systematic review led by Lee Hooper evaluated 67 different clinical signs, symptoms, and simple tests for identifying dehydration in people aged 65 and over. None proved consistently useful. The review went further and named specific tests that should not be used to indicate dehydration in older adults: dry mouth, feeling thirsty, heart rate, urine color, and urine volume. Each of those misses a high proportion of people who are genuinely dehydrated while wrongly flagging people who are fine.

The DRIE study tested the same question inside real care homes. Researchers assessed 188 residents across 56 UK care homes, mean age 85.7, measuring 49 signs and symptoms against serum osmolality as the reference standard. Twenty percent had current dehydration. Forty-eight percent had impending or current dehydration. Not one of the 49 signs usefully separated the dehydrated residents from the hydrated ones.

This is not an argument against observation. It is an argument against building your entire process around symptom hunting. A checklist that asks staff to go looking for tented skin and cracked lips will produce confident documentation and miss half the cases. A checklist built around two different things will perform far better:

  • Measuring and recording actual fluid intake instead of relying on subjective descriptions like “good” or “fair”
  • Tracking changes from each resident’s normal baseline instead of comparing them to a general standard

The DRIE researchers reached a similar operational conclusion. In the absence of a blood test, assume elevated dehydration risk for every resident and focus attention on making sure adequate drinks are supplied and consumed. That principle drives the checklist below.

The Daily Heat-Season Health Check for Facility Staff

Use the checklist in five quick passes, take about five minutes per resident once staff are familiar with the process. During any heat advisory, complete the checklist at least twice a day. If the CDC HeatRisk dashboard shows a level 3 (red) or level 4 (magenta) heat risk for your ZIP code, increase monitoring to three times daily and add an overnight check for high-risk residents.

Pass One: Assess the Room Before the Resident

□  Record the room temperature from a thermometer placed at bed or chair height, not from the hallway thermostat

□  Confirm the reading falls within 78 to 85 degrees, or at least 30 degrees below the outdoor temperature during extreme heat

□  Verify the air conditioning is actively cycling and vents are unobstructed by furniture, curtains, or personal items

□  Note direct sun exposure and confirm blinds or shades were closed before mid-morning

□  Check whether any windows are open while outdoor temperature exceeds indoor temperature

□  Flag west-facing rooms, top-floor rooms, and rooms at the end of a duct run for a second check later in the day

Pass Two: Count Intake, Do Not Estimate It

□  Record the actual volume consumed since the last check-in in ounces or milliliters

□  Compare the running total against the resident’s daily target. ESPEN guidance recommends offering older women at least 1.6 liters of drinks per day and older men at least 2.0 liters, unless a clinical condition requires a different approach

□  Confirm any physician-ordered fluid restriction and document intake in relation to that limit

□  Document refusals, including the reason provided (if known), alternatives offered, and staff follow-up

□  Confirm fluids are accessible and appropriate within reach, at the resident’s preferred temperature and in a cup or container the resident can safely hold or use independently

□  Record intake from high-water foods consumed, such as soup, melon, gelatin, yogurt, or popsicles

□  Flag residents who are significantly below their hydration goal or are more than two scheduled offerings behind by midday or additional intervention

Pass Three: Measure Deviation From This Resident’s Baseline

□  Weigh at the same time each morning, in similar clothing, on the same scale

□  Flag a loss of 2 percent or more from documented baseline weight, or a loss of 2 or more pounds within 24 hours

□  Compare alertness and orientation to that resident’s normal baseline, not to a general standard

□  Note new fatigue, unsteadiness, reduced participation, or a resident who stayed in bed past their usual time

□  Note any change in speech, including slurring or new word-finding difficulty

□  For residents with dementia, note new agitation, withdrawal, repetitive behavior, or sundowning that started earlier than usual

□  Record any fall or near-fall, including a resident who reached for furniture that they normally do not need

Pass Four: Track Output and Position Changes

□  Log number of voids and compare against that resident’s typical pattern

□  Note new incontinence, new constipation, or a change in continence care volume

□  Record temperature, pulse, and blood pressure at the frequency the care plan specifies

□  Where the care plan allows, take blood pressure sitting and standing and note any dizziness on rising

□  Note whether the resident is sweating in conditions where they normally would

Pass Five: Review Medication and Risk Flags

□  Confirm which residents are on diuretics, ACE inhibitors, ARBs, beta blockers, anticholinergics, antipsychotics, or lithium

□  Confirm which residents are bedbound, cognitively impaired, or unable to communicate discomfort verbally

□  Confirm which residents have heart failure, chronic kidney disease, diabetes, or COPD

□  Assign every resident who matches two or more of the above to Place any resident with two or more of these risk factors on the high-risk list for an additional daily check

□  Note residents who declined a scheduled shower, cooling cloth, or move to the cooled common area

One caution worth repeating to staff during in-service training. Nothing on this list is a diagnostic test. A single item does not confirm or rule out dehydration. The value comes from the pattern across passes, and from comparing today’s observations against the same resident’s entries last week.

A Shorter Checklist for Home-Visit Volunteers

Volunteers doing wellness checks on seniors living independently are working with less time, no chart, and no clinical training. The list has to be shorter and it has to avoid asking anyone to make a medical judgment. Use the same ten-item structure during every visit.

□  Read the indoor thermometer and write down the actual number before anything else

□  Confirm the air conditioner or cooling unit is running and producing cold air, not just noise

□  Ask what they have had to drink today, then look at the sink, counter, and recycling for physical evidence

□  Open the refrigerator and check whether food or drinks from your last visit are untouched

□  Ask the same three orientation questions every single visit, such as the day of the week, who visited last, and what they ate for breakfast

□  Note whether they are dressed for the weather, including heavy layers, socks, or blankets on a hot day

□  Ask whether medications were taken on schedule and look for undisturbed pill organizers

□  Ask directly about dizziness when standing and about any falls since your last visit

□  Confirm a working phone is within reach of where they spend most of the day, and that they know who to call

□  Write down what you observed and send it to the same coordinator every time, even when everything looked normal

That last step is more important than it may seem.  A volunteer’s note saying nothing unusual observed becomes valuable the following week if another volunteer documents a change. Reliable baselines only exist when someone consistently records the ordinary days, making it easier to recognize when something is no longer ordinary. 

Escalation: Decide the Three Tiers in Advance

A checklist without clear decision rules just produces documentation. Define what happens after each finding before heat season starts, and print it on the same page as the checklist.

Tier One: Watch and Recheck

Intake behind target, mild lethargy, a single missed offering, or a room running warmer than plan. Log it, correct the immediate cause, and recheck within two hours.

Tier Two: Escalate This Shift

Weight down 2 percent or more, intake well below target for a full day, new confusion or agitation that is out of character, dizziness on standing, a fall, reduced urine output, or a temperature above 102 degrees. Notify the supervising nurse or physician during the same shift and document the response.

Tier Three: Call 911 Immediately

Body temperature above 103 degrees; hot, red, dry or damp skin; a rapid strong pulse; confusion, slurred speech, or loss of consciousness; seizure. This is heat stroke and it is a medical emergency where minutes matter.

While waiting for EMS, move the person to the coolest available space, remove excess clothing, and apply cool wet clothes or a cool bath. Do not give fluids to anyone who is confused, vomiting, or losing consciousness. Be careful with fans as a cooling tool during severe heat. Once the heat index climbs into the high 90s, moving hot air across the skin can raise body temperature instead of lowering it.

Set Baselines Before the Season, Not During It

Every deviation-based system depends on having something to deviate from. May and early June are the window for that work, and most of it is administrative rather than clinical.

  • Document a baseline morning weight for every resident and repeat it monthly.
  • Document each resident’s normal orientation, normal ambulation, normal void pattern, and normal daily fluid intake.
  • Calculate individual daily fluid targets with the physician, especially for residents with cardiac or renal restrictions.
  • Map the building. Log afternoon temperatures room by room across a hot week and identify which rooms run warmest.
  • Service the HVAC system and confirm the backup plan in writing, including who to call, what portable units are on hand, and where residents relocate if cooling fails.
  • Identify local cooling centers and confirm they are current for this year, not carried forward from a previous plan.
  • Run a heat in-service for all staff and document attendance.

Building a resident’s baseline is closely related to the broader skill of recognizing and reporting abnormalities. Staff who already know what normal looks like for each resident will catch heat illness earlier, because they are noticing a change rather than searching for a symptom.

Documentation Is What Gets Reviewed

After a heat-related hospitalization, the question from Community Care Licensing is rarely whether the facility cared. It is what the record shows. Three habits make that record defensible.

Record measurable facts, not adjectives. Fourteen ounces at 10:15 a.m. is a fact. Drinking well is an opinion, and it will not survive review.

Record the negative findings as well. A log that only documents problems does not demonstrate that routine checks were completed on days when no issues were identified..

Record the action, not only the observation. Note what was offered, what was accepted, who was notified, and what they said.

PIN 18-08-CCLD also directs providers to report heat-related illnesses and deaths to the local licensing office, and to contact that office for assistance with evacuations. Know which regional Adult and Senior Care office covers your facility before you need it.

Elderly Heat Stroke Prevention Frequently Asked Questions

What are the early signs of dehydration in elderly adults?

The most reliable early indicators are not physical symptoms at all. They are a drop in measured fluid intake, a weight loss of 2 percent or more from baseline, and a change from that person’s normal alertness, energy, or urine output. Traditional signs like dry mouth, thirst, and skin turgor have been shown in Cochrane research to miss a high proportion of dehydrated older adults, so they should never be the only thing a caregiver relies on.

Why is the skin pinch test unreliable for older adults?

Skin elasticity naturally declines with age, so tented skin may appear in well-hydrated older adults and can be absent in those that are dehydrated. The DRIE diagnostic accuracy study measured 49 signs of dehydration, including skin turgor, against blood tests in 188 care home residents. Researchers found that none of the individual signs reliably distinguished dehydrated residents from those who were adequately hydrated.

How much fluid should an older adult drink each day?

ESPEN geriatric guidance recommends offering older women at least 1.6 liters of fluids daily and older men at least 2.0 liters, which is approximately 7 to 8.5 cups, unless a medical condition requires a different amount. Residents with heart failure or chronic kidney disease may have physician-ordered fluid restrictions. Individual hydration goals should always be confirmed with the resident’s prescribing provider rather than applied as a one-size-fits-all standard.

What temperature is a California RCFE required to maintain during a heat wave?

Title 22, Section 87303(b) requires resident-occupied rooms to be maintained at a comfortable temperature range between 78 and 85 degrees Fahrenheit, or, in areas of extreme heat, at no more than 30 degrees below the outside temperature. Facilities should view this requirement as a compliance minimum rather than a safety target, since 85 degrees is not a safe sustained temperature for frail residents on medications that affect fluid balance.

What is the difference between heat exhaustion and heat stroke in older adults?

Heat exhaustion typically presents with weakness, dizziness, headache, nausea, muscle cramps, and either heavy sweating or cool clammy skin. The person is still alert and oriented. Heat stroke is a medical emergency characterized by a body temperature of 103 degrees or higher; hot skin that may be red, dry or damp; a rapid strong pulse; and changes in mental status such as confusion, slurred speech, or loss of consciousness. Heat exhaustion prompts cooling and close monitoring. Suspected heat stroke requires calling 911 immediately.

Which medications increase heat stroke risk in seniors?

Diuretics, ACE inhibitors, ARBs, beta blockers, anticholinergics, antipsychotics, some antidepressants, antihistamines, and lithium can all impair thermoregulation, fluid balance, or cardiovascular response to heat. CCLD’s heat preparedness notice specifically directs providers to monitor residents on medications that increase the likelihood of dehydration. No caregiver should adjust or withhold a medication because of heat. Flag the resident for closer monitoring and route the question to the prescribing physician.

How often should caregivers check on an elderly person during a heat wave?

At minimum, conduct checks twice daily during a heat advisory. Increase monitoring to three times daily plus an overnight check for high-risk individuals when the CDC HeatRisk dashboard shows a level 3 or 4 forecast for the facility’s ZIP code. Residents who are bedbound, cognitively impaired, on multiple heat-sensitive medications, or living in rooms that retain heat should be monitored more frequently than the facility’s general resident population.

Should you give water to someone showing signs of heat stroke?

No. Someone who is confused, vomiting, or losing consciousness is at risk of aspiration, so fluids should be withheld until emergency medical services arrive. Focus on aggressive external cooling instead: move them to the coolest available space, remove excess clothing, and apply cool wet cloths. Small sips of water are appropriate for heat exhaustion in a person who is fully alert.

Are fans enough to keep an older adult safe during extreme heat?

No. Fans help with air circulation at moderate temperatures, but once the heat index reaches the high 90s, moving hot air across the skin can increase body temperature rather than reduce it. Fans are a supplement to air conditioning, never a substitute for it, and a facility whose cooling plan depends on fans does not have a cooling plan.

What does a California RCFE heat emergency plan need to include?

Per Provider Information Notice 18-08-CCLD, the facility’s emergency plan should include up-to-date emergency telephone contact numbers, contingency plans for air conditioning failures, an evacuation plan for relocating residents to locations such as motels or cooling centers, information about local cooling centers, and a process for reporting heat-related illnesses or deaths to the local licensing office. Administrators should also contact their regional licensing office for assistance with evacuations.

Do RCFEs have to report heat-related illness to Community Care Licensing?

Yes. CCLD’s heat preparedness notice directs providers to report heat-related illnesses and deaths to their local licensing office. Facilities should also follow standard unusual incident reporting requirements for any hospitalization or death, and should retain the daily monitoring logs that document the care provided leading up to the event.

Turn the Checklist Into Trained Practice

A checklist only performs as well as the staff running it. The difference between a facility that catches dehydration on Tuesday and one that calls 911 on Thursday is usually training, not paperwork. Staff need to understand why intake volume matters more than a skin pinch, why baseline deviation beats symptom hunting, and where their authority to escalate begins and ends.

Assisted Living Education offers RCFE Administrator certification training and continuing education courses, including 40 hour and 20 hour programs built for exactly this kind of operational readiness, covering Title 22 compliance, resident health and safety, emergency planning, and staff supervision. Whether you are pursuing your initial RCFE Administrator certificate or completing the 40 hours of continuing education required for recertification, the coursework connects regulation to daily practice.